The combination establishes one of the largest value-based care platforms in the United States dedicated to underserved communities, entering 2027 with nearly 500,000 attributed Medicaid and Medicare lives and $3 billion in managed medical spend across nine states.
The 500k-Member Cohort, Embedded Community Teams, and AI-Driven Care Plans
The merger of Diverge Health and Medical Home Network brings together complementary operational, technical, and clinical models tailored to safety-net healthcare:
Unifying FQHC Networks and Independent Primary Care: Bridges two distinct provider segments that historically operated in silos. While MHN brings more than 15 years of experience managing FQHC networks—having launched one of the nation’s earliest and most successful community health center Medicaid ACOs—Diverge Health brings a proven track record partnering with independent primary care physicians. Entering 2027, the combined entity connects nearly 100 FQHCs and more than 300 independent practices, supported by over 20 payer contracts across nine states.
Demonstrated Actuarial and Engagement Outcomes: Backed by real-world performance metrics. In commercial payer deployments, Diverge’s model delivered a 2% net reduction in population-level Medical Loss Ratio (MLR) alongside a 6% increase in patient primary care visits in 2025, proving that proactive field outreach directly improves quality metrics and keeps patients anchored in primary care rather than emergency rooms.
Embedded Field Teams for Whole-Person Care: Solves the staffing bottleneck that constrains community clinics. Rather than demanding that clinic doctors manage non-clinical social needs, the platform embeds multidisciplinary community health teams directly alongside partner practices. These teams address behavioral health barriers, arrange transportation, coordinate social services, and engage disconnected patients in their homes and neighborhoods.
Proprietary Risk Modeling and Automated Care Planning: Modernizes the data input layer for complex patient populations. Diverge’s machine learning infrastructure ingests multi-source data—including clinical EHR records, Medicaid encounter data, and community social vulnerability indices—to identify “rising-risk” patients before an acute crisis occurs. The system automatically drafts customized, actionable care plans, placing them directly into the hands of local care coordinators to streamline field interventions.
Executive Leadership
Binoy Bhansali leads the combined organization as CEO of Diverge Health, with Cheryl Lulias serving as Co-Founder and President of MHN PBC. The platform is backed by prominent healthcare venture capital and growth equity firms, with Oak HC/FT joining the board of directors alongside Triple Aim Partners and GV (Google Ventures).
“Value-based care is notoriously hard, especially in Medicaid, but strengthening our country’s primary care backbone and supporting their patients to live their healthiest lives is a moral imperative,” said Binoy Bhansali, CEO and Co-Founder of Diverge Health. “Together, we are proving that succeeding in value-based care is very much possible if you support these practices with the right infrastructure, community health teams, and data.”
You’re reading the web edition of STAT’s Health Tech newsletter
Adobe
Mario covers technology in health care, including FDA regulation of artificial intelligence; how Medicare pays for health tech; the use of AI in clinical care; mental health chatbots; and consumer wearables. He’s also the co-author of the free, twice weekly STAT Health Tech newsletter. You can reach Mario on Signal at mariojoze.13.
You’re reading the web edition of STAT’s Health Tech newsletter, our guide to how technology is transforming the life sciences. Sign up to get it delivered in your inbox every Tuesday and Thursday.
Good morning health tech readers!
I’m getting on a train to Boston in couple of hours for STAT Summit. See some of you soon.
Mario covers technology in health care, including FDA regulation of artificial intelligence; how Medicare pays for health tech; the use of AI in clinical care; mental health chatbots; and consumer wearables. He’s also the co-author of the free, twice weekly STAT Health Tech newsletter. You can reach Mario on Signal at mariojoze.13.
Mount Sinai Health System researchers launched bioengineered human brain and cardiovascular tissue models into orbit aboard the SpaceX CRS-35 Commercial Resupply Services mission to the International Space Station (ISS).
Developed across Mount Sinai’s Departments of Stem Cell Biology and Regenerative Medicine, Neuroscience, and Surgery, alongside the Cardiovascular Research Institute, the dual investigations pair patient-derived stem cell organoids and microfluidic “organ-on-a-chip” systems with automated space biology hardware engineered by Space Tango in collaboration with NASA.
Leverages the microgravity and elevated radiation environment of low Earth orbit (LEO) as an accelerated biological model to study the cellular mechanics of human aging, neurodegeneration, and cardiovascular decline.
The Biological Payloads: miBrain and µCVchip
The mission deploys two distinct human tissue platforms into low Earth orbit to assess neurological signaling, vascular dynamics, and cellular stress in real time:
The miBrain Platform (Neural Aging & Genetic Susceptibility):
Cellular Composition: Derived from human induced pluripotent stem cells (iPSCs), the miBrain model reconstructs human brain tissue architecture by incorporating all major cerebral cell lineages—including neurons, astrocytes, microglia (immune cells), and functional microvasculature.
Orbital Science Objectives: Led by Joel W. Blanchard, PhD, the project evaluates how microgravity and elevated space radiation alter neural cellular communication, blood-brain barrier permeability, and neuroinflammatory injury markers.
Terrestrial Disease Modeling: Crucially, the mission tests how high-risk neurodegenerative genetic variants—specifically the APOE4 allele, the strongest genetic risk factor for late-onset Alzheimer’s disease—influence cellular aging kinetics and susceptibility to environmental stressors, comparing orbital degradation rates against baseline Earth controls.
The µCVchip Platform (Functional Cardiovascular Organoids):
Automated Microfluidic Architecture: Co-led by Kevin D. Costa, PhD, and David Sachs, PhD, the project sends two microfluidic chips containing up to 16 beating human cardiovascular organoids grown from healthy stem cells.
Autonomous Orbit Testing via Space Tango CubeLab: Building upon a 2023 preliminary cell viability mission aboard SpaceX CRS-29, the CRS-35 hardware integrates automated electrical pacing, hydraulic pressure testing, high-resolution microscopic imaging, and programmatic fluid sample collection to track cardiac contractility and vascular remodeling under continuous microgravitational unloading.
Translational Cardioprotection: The data aims to isolate cellular mechanisms behind spaceflight-induced cardiac deconditioning and vascular stiffness, informing novel therapeutic targets for heart failure and vascular disease in aging terrestrial populations.
The company said the new lens uses its proprietary ENLIGHTEN NXT optical technology which delivers the lowest light scatter and highest reported light utilization of any trifocal IOL.
According to Alcon, PanOptix Pro provides 94 per cent light utilisation, compared to a theoretical maximum utilization of 96 per cent for diffractive optics.
“PanOptix Pro offers powers ranging from +6.0 through +30.0 diopters (in 0.5 diopter increments), +31.0 through +34.0 diopters (in 1.0 diopter increments) with a +2.17 diopter intermediate and a +3.25 diopter near add power,” Alcon added.
Join the community of 2M+ industry professionals.
Subscribe to Newsletter to get latest insights & analysis in your inbox.
All about ETHealthworld industry right on your smartphone!
Pune: AI-led medical tourism platform, CureMeAbroad, has expanded into Australia with a network of experience centres across multiple locations.
The company said it has signed an MoU to anchor the rollout with 40 experience centres planned to open across Australia, the US and the UK.
The company said its first centre in Australia will open in Brisbane giving patients an in-person place to begin their treatment journey.
They will connect to CureMeAbroad’s digital platform, which gives patients access to more than 400 partner hospitals across Turkey, Thailand, India, Mexico, Georgia and other destinations.
Join the community of 2M+ industry professionals.
Subscribe to Newsletter to get latest insights & analysis in your inbox.
All about ETHealthworld industry right on your smartphone!
New Delhi: People who developed an early onset of Alzheimer’s disease — before turning 65 — displayed symptoms and conditions different to those in late-onset Alzheimer’s, accumulating a wide range of health problems, particularly during the five years preceding diagnosis, a study has found.
Researchers from the University of Oulu and the University of Eastern Finland said the group is more likely to experience depression, dizziness, headaches, traumatic brain injuries, epilepsy, cerebrovascular disorders, thyroid diseases and problems related to heavy alcohol use.
Tinnitus (ringing in ears) and hearing loss were already more common six to ten years before diagnosis, findings published in the journal Alzheimer’s and Dementia: The Journal of the Alzheimer’s Association showed.
However, cardiovascular risk factors traditionally associated with Alzheimer’s disease were found to be no more common among those diagnosed at working age, compared to age- and sex-matched healthy people.
Cardiovascular risk factors, alongside advanced age, are among the best-known risk factors for the neurodegenerative disease, the researchers said.
“Our findings support the view that early-onset Alzheimer’s disease is not simply a younger-age version of late-onset Alzheimer’s disease. Rather than the familiar cardiovascular risk factors, we observed a range of other health problems becoming more common as diagnosis approached,” lead researcher Johanna Kruger, adjunct professor from the University of Oulu, said.
The researchers also found no significant differences in morbidity 11 to 15 years before diagnosis, suggesting that identifiable changes begin to emerge mainly closer to disease onset.
The findings indicate that early-onset Alzheimer’s disease may involve mechanisms that differ, at least in part, from those underlying late-onset Alzheimer’s disease, they said.
Healthcare utilisation was found to have increased markedly during the five years leading up to diagnosis, alongside a growing burden of health conditions. The steepest increase in healthcare visits was seen to occur during the final year before Alzheimer’s disease was diagnosed.
The study’s findings are based on patient data from memory clinics at Oulu University Hospital and Kuopio University Hospital, combined with nationwide health register data.
The study included 407 people with early-onset Alzheimer’s disease, whose health records were compared with those of more than 4,000 age- and sex-matched people without the neurodegenerative disease. Diseases and health conditions were examined that occurred during the 15 years preceding an Alzheimer’s disease diagnosis.
“EOAD (early onset Alzheimer’s disease) patients had higher prevalence of vertigo, depression, headache, delirium, brain injuries, thyroid disorders, alcohol-related disorders, epilepsy, strokes, and otorhinolaryngologic diseases 1-5 years before diagnosis,” the authors wrote.
UnitedHealth raised its 2026 earnings guidance and outperformed analyst expectations for the third time this year, suggesting its financial turnaround is sustainable.
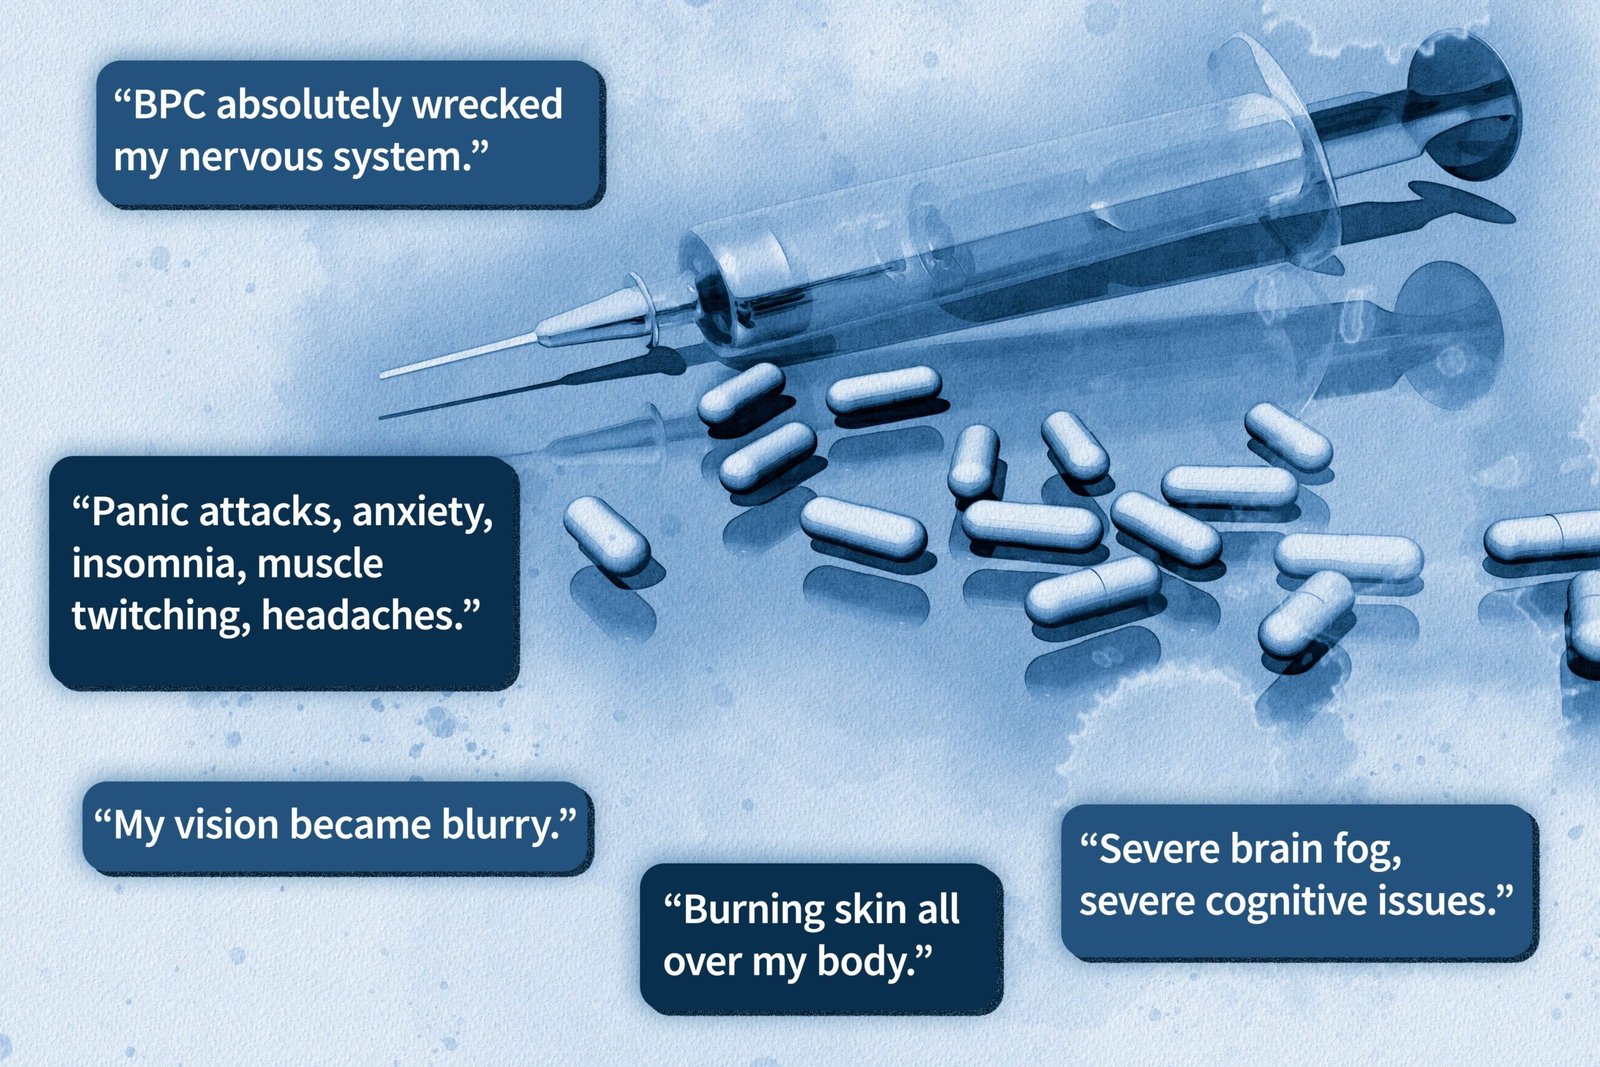
After the third day of squirting an experimental drug up his nose, Dylan Meetze felt horrible.
“It was like I was underwater, like it took the most to do anything,” he said.
Meetze stopped taking the drug but endured fatigue and anxiety for months afterward, and his eyes and muscles twitched, he said.
He had taken BPC-157, a peptide drug popularized by podcasts about wellness, longevity, and what’s called “body optimization.” “Peptide” is a general term for substances that are smaller than proteins but composed of the same building blocks. Dozens of peptide drugs, including insulin and GLP-1 weight loss medicines, have garnered approval by the Food and Drug Administration. But BPC-157 and many others have not because they haven’t undergone clinical trials.
This fact hasn’t stopped online influencers from promoting them as remedies for muscle injuries, gut issues, covid, and more. Use of BPC-157 is growing in the U.S., particularly among white males, according to a new analysis of millions of de-identified electronic health records. Since 2020, the analysis, which hasn’t yet been published in a peer-reviewed journal, found that more than 1,000 people told doctors they had used the drug.
Meetze said he decided to take BPC-157 after listening to Andrew Huberman, a Stanford neuroscientist with more than 16 million followers on YouTube, Instagram, and TikTok, who talks up peptides frequently on his podcasts. Studies in mice suggest that BPC-157 helps muscles heal and has “very high safety profiles,” Huberman has said, “at least, with respect to the lethal dosing.” His guest on one episode, Craig Koniver, a doctor who sells peptides through his wellness clinic, called BPC-157 “super safe” and recommended it for “anyone who’s working out on a regular basis.” Koniver did not respond to requests for comment.
Huberman didn’t respond to multiple queries from KFF Health News, but an automatic reply linked to a disclaimer on his Huberman Lab website that says the podcast doesn’t constitute medical advice: “Any reliance on information provided through the podcast is solely at the user’s own risk.”
Hoping BPC-157 might help him advance as a weightlifter, Meetze said he bought the drug last year from an online vendor, Researchem. A chemical supply company with that name sells experimental peptides through its website, warning that the substances are “solely for laboratory research” and are “not intended for human consumption.” (It lists an address in Hillsboro, Oregon, that corresponds to a shared office space. A receptionist at the space said Researchem wasn’t registered there, and multiple queries from KFF Health News to the email address listed on the website went unanswered.)
Companies are required to warn that experimental peptides, which haven’t been approved by the FDA, are for research use only. But many companies may soon be permitted to drop the warning because of a push by health secretary Robert F. Kennedy Jr. to lower barriers to their use. He and other leaders of the Make America Healthy Again movement have promoted peptides as a way to improve the country’s health.
On the social media platform X, before he took the helm at the Department of Health and Human Services, Kennedy vowed to end the “aggressive suppression” of “peptides, stem cells, raw milk” and “anything else that advances human health and can’t be patented by Pharma.” (In fact, peptides are heavily patented.)
He has repeated the pledge since taking office. On Joe Rogan’s podcast early this year, Kennedy said he was a “big fan” of peptides and wanted to make many of them “more accessible.” On a podcast with the co-chair of the MAHA Action committee, Gary Brecka, Kennedy said the FDA’s role should be to assess science, “but not tell people and not tell physicians what they can and cannot prescribe.”
“If you want to take an experimental drug,” he added, “you ought to be able to do that.”
Health secretary Robert F. Kennedy Jr. spoke on the Joe Rogan Experience podcast in February, saying he’s a fan of peptides and has used them “on a couple of injuries.” (Clip from YouTube video)
This summer, Kennedy’s health department appointed doctors with financial stakes in the peptide industry to a panel that advises the FDA. At an FDA meeting in July, the new appointees voted to ease restrictions on six experimental peptides, including the trendy compounds BPC-157, TB-500, and MOTS-c. Specifically, they advised adding these peptides to a list, called 503A, that would allow specialized pharmacies to make the drugs for human use, even though the FDA hasn’t approved them.
In an email, HHS spokesperson Emily Hilliard wrote that every committee member satisfies the FDA’s ethics requirements. “FDA — not podcasts or politics — determines which substances qualify for inclusion on the 503A Bulks List,” she wrote. The FDA has yet to issue a final decision.
The vote went against FDA scientists who presented research on the six peptides, concluding there wasn’t enough evidence to show they improved any condition. Furthermore, the scientists highlighted a potential for liver damage, allergic reactions, or other serious consequences.
“People are saying this is about medical freedom — putting decisions back in the hands of patients,” said Reshma Ramachandran, a regulatory science researcher at Yale School of Medicine. “But what we see in practice is that incentives aren’t actually centered around patients. They’re centered around selling products.”
Scientists also warned that drugmakers would be reluctant to invest millions of dollars into clinical trials on peptides if they could be sold without FDA approval.
“The chances of clinical trials getting done now are diminished,” said Eric Topol, executive vice president of Scripps Research, a biomedical science institute in San Diego. “We will have more people who are prey to predators that will sell, sell, sell.”
A lack of data leaves consumers in the dark.
Meetze sought help on Reddit, where people post about pain, headaches, vision problems, and a lack of motivation after taking experimental peptides. Peptide enthusiasts often comment on these posts with skepticism, attributing a person’s problems to contaminated products, preexisting conditions, or misuse of the drugs. The online vitriol in the Reddit conversations can be intense, so Meetze welcomed an invitation to join a private group on the social platform Discord in which people with BPC-157 side effects tried to figure out what happened to them and how to fix it.
“There are millions of success stories with these peptides,” Meetze said, “but no one wants to believe that this wrecks some of our lives.”
Experimental peptides are often sold at longevity, wellness, and “performance medicine” clinics — even though they haven’t been proved safe and effective in clinical trials. (Amy Maxmen/KFF Health News)
Wolverines and Migraines
One member of the private side-effects group, a 46-year-old software engineer named Dominik E., said he got an excruciating migraine within days of taking BPC-157 with TB-4, another unapproved peptide — a combination called the “Wolverine Stack” because of its purported ability to heal wounds rapidly, like its namesake Marvel superhero.
“My left eye started throbbing really badly, and the left side of my face became numb,” he told KFF Health News, which agreed to only partially identify him and others interviewed for this article who were concerned about divulging sensitive health information.
After two months of migraines, Dominik said, the pain eased, but his face felt inflamed. “It is a total nightmare,” he said.
“I’m afraid how people will judge me,” said Lois S., a woman who works at a Michigan elementary school. She hoped BPC-157 and another unapproved peptide, retatrutide, would help with weight loss, but she stopped taking the treatment when she felt pain.
“I sought out this substance from a lab that clearly labeled it not for human use, purchased a syringe, and injected this in my kitchen,” she said. “That belies all logic about what a normal person would do.”
Peptide proponents argue that shoddy manufacturing — not the peptides — causes harm. Therefore, they say, the FDA must protect the public by allowing doctors to prescribe peptides made for human use by pharmacies that specialize in compounding medicines. Typically, compounding pharmacies manufacture alternatives to FDA-approved drugs so a patient can, say, get a liquid version of a drug that the original manufacturer makes only as pills.
Adding unapproved peptides to the FDA’s list of compoundable drugs would mark a departure from the list’s purpose, said Peter Lurie, a former FDA official who now directs the advocacy group Center for Science in the Public Interest. He noted that federal and state oversight for compounding pharmacies is often lax, and they’ve been cited for contamination.
Furthermore, he added, the move would mislead consumers into thinking they’re buying drugs backed by clinical trials. People promoting peptides often point to promising laboratory research as evidence. Rats with spinal injuries regained tail mobility after BPC-157 injections, for example, and old mice given the experimental peptide MOTS-c could run longer. On average, however, fewer than 10% of substances that show promise in animal studies prove effective in clinical trials.
“A lot of this pseudoscience stuff sounds deeply impressive — inflammation this and telomere that — but at the end of the day, none of it really matters,” Lurie said. “You’ve got to show clinical benefit in humans: Does it work?”
Peptide promoters lean on anecdotes, often without verifiable numbers. In a podcast recorded at the White House, the MAHA influencer Brecka said: “Twenty million people have been prescribed these things without adverse events.” His guest on the episode, Brigham Buhler — who is the co-author of The Peptide Revolution and owner of a compounding pharmacy that sells peptides and a clinic, Ways2Well, that prescribes them — told Brecka that none of its 75,000-plus patients had reported adverse events from peptides.
Buhler cited even higher numbers in the movie MAHA Uncensored, a documentary featuring Kennedy and other leaders of the MAHA movement and that bears the MAHA trademark. In the segment on peptides, Buhler said: “Having treated literally hundreds of thousands of people through our compounding pharmacy, we’ve never had a major adverse event.”
Topol asks why those boasting success haven’t conducted clinical studies. “If influencers and companies really believe these peptides are helping people,” Topol said, “then they should put their profits back into rigorous research.”
Chris Woodward, a spokesperson for Brecka and his company, the Ultimate Human, said in an email that the health and wellness issues discussed on Brecka’s podcast do not constitute medical advice. “Mr. Brecka consistently advises his audience to consult a licensed physician,” Woodward wrote. Buhler did not respond to requests for comment.
On an episode of his Ultimate Human podcast recorded in the White House, Gary Brecka, a co-chair of the MAHA Action committee, promoted peptides that haven’t been approved for safety and effectiveness by the FDA.
Not all anecdotes are rosy. At an antiaging conference last summer in Las Vegas, two women were rushed to the hospital and intubated after being injected with experimental peptides and vitamins, according to citations that Nevada’s state pharmacy board issued against the doctor running the booth and his colleagues for prescribing and administering drugs without a state medical license.
An FDA database for adverse events contains concerning reports. Although the database can’t prove that a drug, vaccine, or medical device caused harm — the reports are brief, unverified, and voluntary — it signals issues worth exploring. A 36-year-old woman was hospitalized in December after taking the experimental peptide BPC-157 for weight control and a skin disorder, for example, and a 48-year-old man was hospitalized with a “life-threatening” condition after taking the peptide.
FDA scientists presented some of these reports at the July meeting and flagged worrisome outcomes in animal experiments, such as a 2020 study revealing signs of liver toxicity in rats and dogs injected with BPC-157.
Brian Lee, a liver disease specialist at the University of Southern California, was among the panel’s minority who voted against easing restrictions. Without clinical studies, he said, afflictions that take time to develop, like liver damage and cancer, might not be spotted for years: “I think this endorsement can be potentially harmful, and I cannot in good conscience vote ‘yes.’”
The panel’s newcomers disagreed. “I do not believe the FDA made a good case on issues with safety with BPC,” said Kris Wusterhausen, founder of an antiaging company in Texas, the Resurge Clinic, which sells a BPC-157 product for $149.
“Once you’ve seen the effects of BPC,” he said, “you can’t unsee it.”
At an FDA meeting in July, Brian Lee, a liver disease specialist at the University of Southern California, voted against easing restrictions on the experimental peptide BPC-157, citing safety concerns.
Awaiting Trial
Deepak Srivastava, president of the Gladstone Institutes in San Francisco, designed a clinical trial two decades ago to see if a peptide he studies, TB-4, could repair tissue after a heart attack. Before enrollment, people volunteering for the study would be screened for early signs of cancer because TB-4 triggers vessel growth and cell migration, which might exacerbate malignant growths. He worries about the FDA panel’s vote to ease restrictions on a derivative of TB-4, before such trials have been completed, saying, “You need to have a healthy respect for the fact that drugs can be harmful.”
Pinchas Cohen, a peptide researcher at the University of Southern California, was less cautious, saying the FDA buzz might drive investors to fund trials. He’s seeking support to bring a peptide his lab identified, MOTS-c, to market. It’s “un-ideal” for people to take unproven drugs, Cohen said, but that’s what’s happening: “The world is changing and people like me need to accept that this is the new reality and find ways to make it as safe as possible.”
In the meantime, people like Meetze resort to podcasts and online forums for advice. His symptoms faded after a year, but he still had spells of feeling “zero emotions.”
Peptide users describe this condition as anhedonia. It’s come up on Huberman’s podcasts.
Huberman occasionally mentions other potential peptide risks, like cancer, sprinkling them into advice on how to take them. Take a 2024 episode with 1.2 million views: “I do not think that BPC-157 is not without its quote-unquote ‘side effects,’” Huberman says. “If you’re going to go down this path of taking BPC-157, I would encourage you to take the minimal effective dose, to not simply do it every day, and certainly to not do it continuously, and of course to monitor your other health metrics for anything that could potentially resemble cancer or tumor growth, because obviously stimulating angiogenesis for wound repair sounds like a great thing, recovering and being able to do your workouts or play your sport, or move about more comfortably, of course, a wonderfully attractive thing to do.”
“Isn’t that what we all want? But obviously not with the trade-off of growing a tumor,” he said, before interrupting the discussion to advertise a supplement company sponsoring the show.
When Carol Daniel, a veteran broadcast journalist who lives near St. Louis, was diagnosed with thyroid cancer in 2022, her husband encouraged her to seek a second opinion. She was worried that consulting another doctor might seem like a betrayal.
Daniel said she wondered: “Am I cheating on him? Am I going behind his back? Am I acting like I don’t trust him by seeking a second opinion?”
Many patients find themselves in this position, but family medicine physician Jen Caudle said patients shouldn’t feel awkward about asking for a second opinion. In fact, in her practice in New Jersey, she encourages people to have open conversations with their care team.
“We shouldn’t be offended,” Caudle said. “We should support you.”
Patients can also think of their primary care provider as the quarterback of their care team, Caudle said, and ask that doctor for help navigating opinions or diagnoses from specialists.
Cara Anthony and Blake Farmer, hosts of the HealthQ series, spoke with Caudle about the sometimes-awkward art of asking for a second opinion.
The QTip:
Your primary care provider can help you navigate first and second opinions from specialists.
Katherine Ruppelt andEmily Siner at Nashville Public Radio contributed to this report.
HealthQ is a health series from reporters Cara Anthony and Blake Farmer, approachable guides to an unapproachable healthcare system. It’s a collaboration between Nashville Public Radio and KFF Health News.
Bengaluru: Amid growing calls for transparency in healthcare costs, the Karnataka Food Safety and Drug Administration has ordered all hospitals, distributors and retailers in the state to display base price (actual procurement cost to hospitals / hospital pharmacies) and Maximum Retail Price (MRP) on all bills for medicines, medical devices and consumables.
The move follows mounting scrutiny over the significant difference in landing/base price and the MRP printed on medicines, medical devices and consumables. In several cases, patients are billed at or near MRP without any transparency about the actual acquisition cost, Karnataka FDA said in the circular dated October 1, 2026.
Under the new directive, hospitals must issue an itemised bill showing each medicine, device, implant and consumable separately starting November 1.
For every line item, the bill must state the product name, with generic and brand names where applicable, along with the batch number and the manufacturing and expiry dates.
Bills must also show the landing or base price, exclusive of taxes, the MRP as printed on the pack or notified by the National Pharmaceutical Pricing Authority (NPPA), the price charged to the patient, and any applicable taxes not already included in the MRP.
The price charged to the patient cannot exceed the MRP, the regulatory body noted.
The state FDA also directed hospitals to put up notices at billing counters, pharmacy counters and admission desks informing patients of their right to see the landing price and MRP on their bills, and publish this information on their websites where available.
It added that records of purchase invoices, landing prices and billing details must be maintained for at least three years for inspection and barred hospitals and institutions from charging above the MRP printed on the pack or above the ceiling price notified by the NPPA.
The order applies to all government, private and trust hospitals, nursing homes, clinics, day-care centres and diagnostic centres, covering both in-patient and out-patient services.
It also covers carrying and forwarding (C&F) agents, stockists, distributors, wholesalers and retailers licensed with the department.
Responding to the Karnataka FDA’s move, the Association of Indian Medical Device Industry (AiMeD) welcomed the initiative but pushed for the tracking of prices across the entire supply chain.
Mr. Rajiv Nath, Forum Coordinator, AiMeD, said: “We appreciate the Karnataka Government’s efforts to bring greater transparency to healthcare billing and trade margins. While disclosure of procurement cost and MRP at the hospital level is a useful first step, it captures only the margin at the final point of supply. For effective policy intervention and identification of where excessive mark-ups may arise, the entire value chain needs to be mapped transparently from 1st post of sale when GST is initially applied on import landed price or manufacturer’s selling price through entire supply chain to the patient. End-to-end visibility of ensuring MRP and transaction value captured at invoice at each stage of supply chain will help ensure that corrective measures are evidence-based, fair and focused on the actual source of price escalation.”
Join the community of 2M+ industry professionals.
Subscribe to Newsletter to get latest insights & analysis in your inbox.
All about ETHealthworld industry right on your smartphone!