Category: Digital Health & Technology

  • How consumer tech company Whoop is building for Medicare patients

    How consumer tech company Whoop is building for Medicare patients

    Whoop has never been known for marketing to an older population. Performance athletes headline ads for the wearable company, which aims to turn continuous streams of physiological data into useful insights for behavior change — mostly, for a young, fit customer base.

    But this year, Whoop became one of the first consumer wearable companies to be accepted into Medicare’s ACCESS program, making it available at no cost to many traditional Medicare patients ages 65 and up. On Wednesday, at the STAT Summit in Boston, Whoop’s newly appointed chief medical officer Ami Bhatt spoke about how the company is moving to build experiences — and demonstrate outcomes — for a very different population.

    “Number one on our roadmap — and I think I’m allowed to say this, if I’m not, I’m saying it — is simplification of the app,” said Bhatt, who previously chaired the Food and Drug Administration’s digital health advisory committee and served as the American College of Cardiology’s chief innovation officer. Surveys suggest, said Bhatt, that even members of the Silent Generation, who are older than 80 today, trust their clinicians with their data. “It’s not that they’re averse to giving data,” she said. “It’s how easy can we make it for that population to be able to share their data.” 

    Bhatt said that Whoop, which recently raised $575 million from investors including Mayo Clinic and the sovereign wealth fund of Qatar, is working with the National Council on Aging and AARP to think about how to personalize the product to older adults’ individual priorities. “For each of us, how we feel, how we perform, how we age, we have our own goals,” said Bhatt. “The thing is, we don’t want to decide for you what that is.”  

    The goals are less diffuse for the 10-year pilot ACCESS program, which published a directory of initial participants last month. Through those 55 companies, Medicare patients can access chronic condition management for little or no cost — Whoop serves patients with high blood pressure, high cholesterol, obesity, and prediabetes — and Medicare will pay the companies based on their health outcomes. Whoop will provide patients with a wearable, a 12-month subscription to its app, and access to clinicians who can help them make sense of their data and offer advice.

    “The goal is, how do we bring technology closer to the patient, but not put the cost on the patient — rather, put the demand on the company,” said Bhatt. “Whoop takes responsibility for, in 12 months, I am going to make these people better. I’m going to show you outcomes in the Medicare population who have these risk factors to demonstrate that my technology can help them engage in their own health.” To receive full payment under the ACCESS model, Whoop will be required to show that it improved or controlled measures tied to its patients’ chronic conditions, including blood pressure, hemoglobin A1C, and low-density lipoprotein cholesterol.

    Bhatt said it was her role to help the company — which until recently focused on selling a product intentionally binned in the wellness category — develop and demonstrate those kinds of outcomes that bring them closer to clinical practice. The company just this year announced the ability for users to discuss their wearable data with clinicians, shortly before the FDA closed its warning letter that had initially said Whoop’s blood pressure-estimating feature qualified as a medical device — not a wellness feature. 

    While Whoop demonstrates good patient engagement, said Bhatt — users check the app eight times a day, on average — research into the original “wearable” for diabetes, continuous glucose monitors, suggests that engagement doesn’t necessarily translate to better health outcomes. 

    “In order to actually create personalized health at a population level, you need to start thinking about outcomes,” said Bhatt. “Can we show that we decrease blood pressure by five millimeters of mercury in individuals on Whoop — which, by the way, we have shown — so that we can say, hey, the outcome of cardiovascular disease and stroke, we know that outcome is better.” 

    At the same time, Bhatt said, the utility of continuous data is limited within the traditional health care system. As a practicing physician, “I had some really great patients who would print out binders of their wearable data,” she said. “This is me: I love this data. And I’d be like, ‘Oh, God.’” Despite her interest and the patient’s engagement, it was impossible to handle in a 20-minute visit.

    Ultimately, Bhatt imagines Whoop could help solve that problem, perhaps by delivering contextualized reports to clinicians that summarize a patient’s continuous data along with key points from their own journaling entries and interactions with their Whoop app coach. “When you put that together and you actually have a comprehensive report you can give to a clinician, now your clinician says, ‘Oh, that’s what I needed.’” 

  • Zocdoc Acquires Sohar Health: Expanding Care Access Infrastructure and Automated Insurance Verification

    Zocdoc Acquires Sohar Health: Expanding Care Access Infrastructure and Automated Insurance Verification

    Zocdoc Acquires Sohar Health: Expanding Care Access Infrastructure and Automated Insurance Verification

    What You Should Know

    • Healthcare scheduling and access infrastructure leader Zocdoc announced that it has officially acquired Sohar Health, an automated insurance benefits eligibility and discovery technology company (the transaction closed on October 2, 2026).
    • Marks a historic corporate milestone: this transaction represents the first corporate acquisition in Zocdoc’s nearly 20-year operating history.
    • Accelerates Zocdoc’s strategic transformation from a standalone consumer appointment marketplace into an omnichannel “healthcare access infrastructure” layer that powers real-time provider discovery and booking wherever patients initiate search.

    Transaction Mechanics and Partner Synergy

    The acquisition formalizes a deep technical collaboration established over the preceding year. Zocdoc initially selected Sohar Health as its core insurance verification partner in 2025 following an extensive evaluation of legacy clearinghouses and modern eligibility APIs. Millions of patients have already verified coverage using Sohar’s underlying technology inside Zocdoc.

    Unlike legacy eligibility platforms that require patients to input precise group numbers, subscriber IDs, and obscure payer portal codes, Sohar utilizes minimal demographic inputs—such as a patient’s legal name and date of birth—to programmatically surface active coverage, verify benefits, and confirm in-network tiering in real time. Operationally, Sohar will continue to operate without platform disruption, retaining its brand identity, product suites, leadership team, and independent commercial book of business alongside its deep integration into Zocdoc’s core infrastructure.


    Technical Capabilities and Standalone Enterprise Reach

    Founded in 2023 by physician Ashish Mandavia, MD, and software engineer Lucas Gordon, Sohar has established significant density across modern digital health and behavioral health platforms. Its platform connects to more than 1,000 commercial, Medicare Advantage, and Medicaid health plans nationwide via modern REST APIs.

    The software automates real-time insurance discovery, eligibility and benefit checks, network participation status, and patient out-of-pocket cost estimation prior to care delivery. Beyond Zocdoc, Sohar’s technology powers front-end patient intake, coverage discovery, and intake revenue integrity for leading scaled behavioral health networks, including BetterHelp, Headway, Rula, and Talkiatry.


    Expanding the “Care Access Network” Beyond the Marketplace

    Zocdoc’s inaugural acquisition reflects key strategic shifts across digital health distribution, patient access, and front-end revenue cycle integrity. First, it directly powers Zocdoc’s headless infrastructure play through the Care Access Network. Earlier in October 2026, Zocdoc announced the launch of its Care Access Network, decoupling its underlying scheduling engine, provider registry of over 200,000 providers across 200-plus specialties, and calendar synchronization rails from its native website and mobile app. By embedding real-time provider booking directly into third-party surfaces—including Gemini, Amazon Health AI, Yelp, Healthgrades, and Blue Shield of California—Zocdoc is positioning itself as the universal operating layer for healthcare appointment booking. Acquiring Sohar provides Zocdoc with the proprietary eligibility engine required to instantly verify coverage across all third-party AI and consumer endpoints.

    Second, it eliminates upstream billing friction. In line with the industry-wide push toward proactive revenue cycle management, eliminating administrative waste requires catching errors upstream before care takes place. Front-end eligibility errors represent one of the largest single drivers of initial claim denials. By validating coverage and network tiering at the exact millisecond an appointment is booked, Zocdoc and Sohar intercept denials before patient records reach the practice management system.

    Third, it reinforces the zero-input consumer standard. Consumer adoption succeeds when digital tools reduce friction rather than add administrative paperwork. Sohar’s ability to locate coverage using only a name and date of birth removes the cognitive hurdle of physical health plan cards, significantly lifting search-to-booking conversion rates for provider practices.

    Finally, the deal underscores broader market consolidation momentum. Healthcare platforms are increasingly transitioning from point-tool buyers to platform consolidators, bringing proprietary infrastructure in-house to protect unit economics and build enterprise moats.


  • Labcorp Partners with Thrive Global to Launch Thrive 5 Health Test: ApoB, hs-CRP, and HbA1c Paired with Behavior Change

    Labcorp Partners with Thrive Global to Launch Thrive 5 Health Test: ApoB, hs-CRP, and HbA1c Paired with Behavior Change

    Labcorp Partners with Thrive Global to Launch Thrive 5 Health Test: ApoB, hs-CRP, and HbA1c Paired with Behavior Change

    What You Should Know

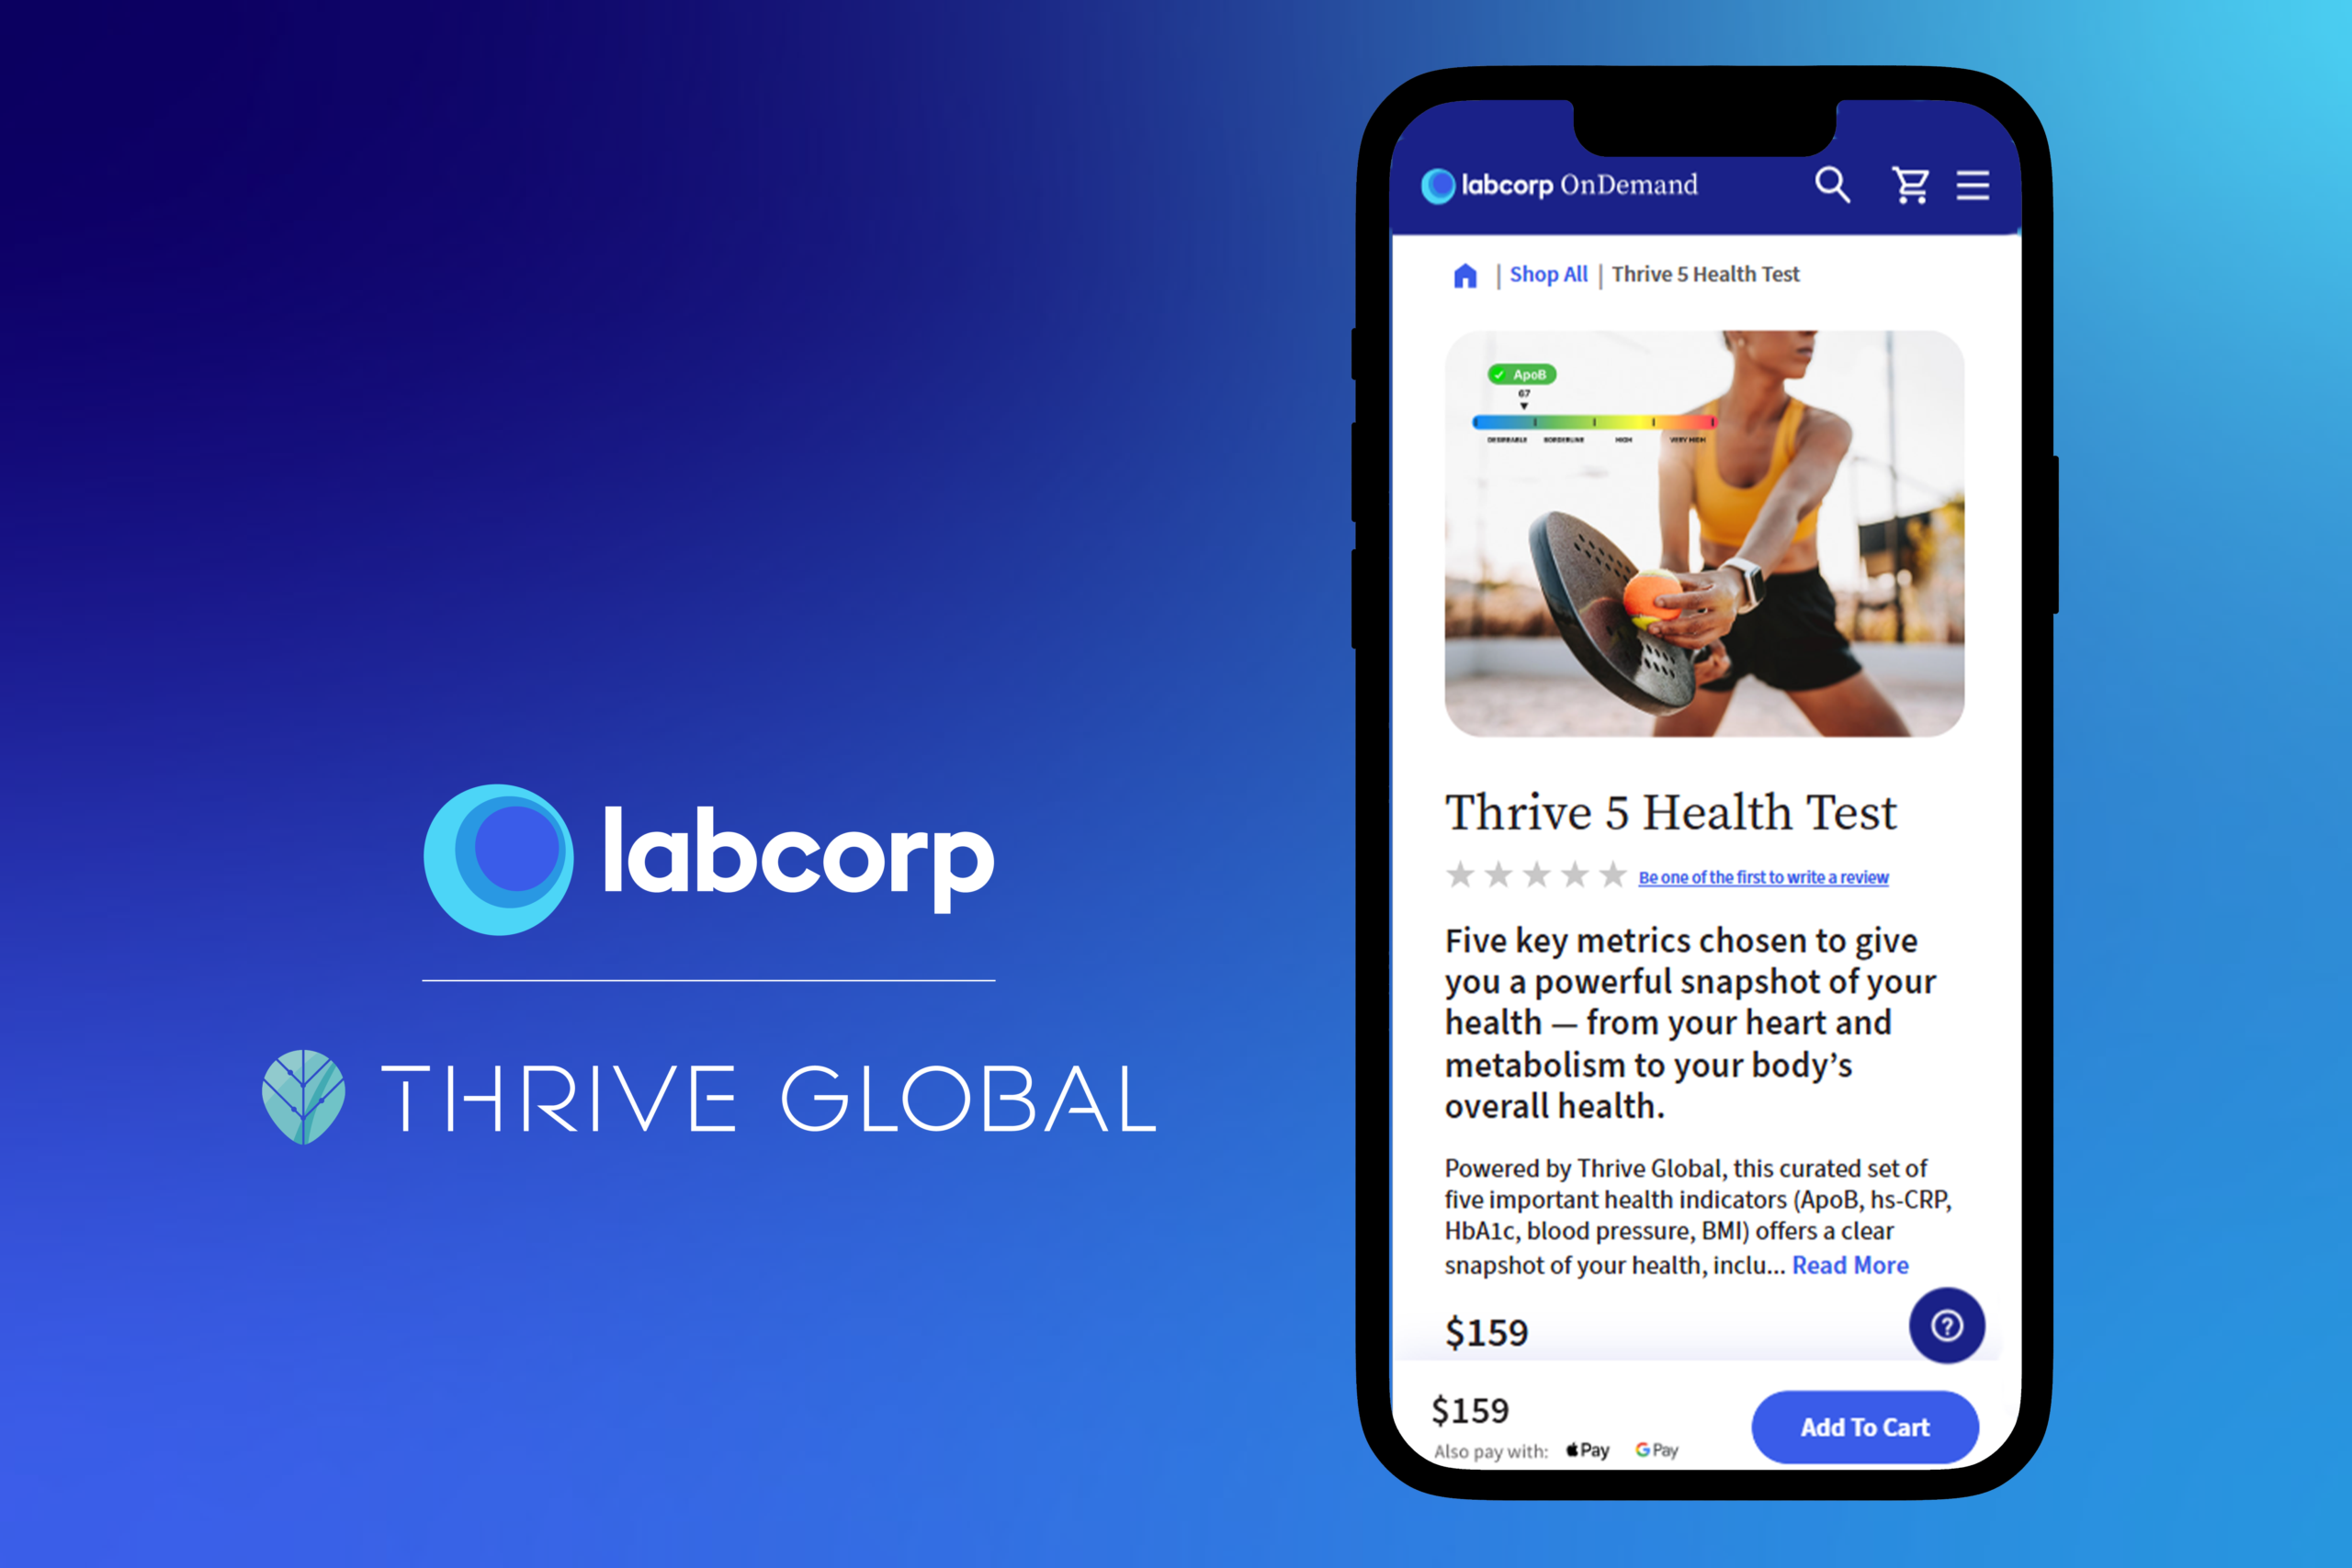
    • Diagnostic laboratory provider Labcorp announced the commercial launch of the Thrive 5 Health Test, representing the first diagnostic lab panel offered in strategic collaboration with Arianna Huffington’s behavior change technology enterprise, Thrive Global.
    • Directly targets the “actionability gap” in consumer health testing: while direct-to-consumer lab kits frequently return dense biochemical reference ranges without behavioral context, the Thrive 5 test translates clinical biomarkers into daily habit modifications.
    • Available via Labcorp OnDemand, the offering represents the first clinical diagnostic product integrated directly with Thrive Global’s habit-formation methodologies, combining five validated cardiometabolic markers with tailored, daily behavioral micro-actions.

    The Clinical Biomarker Core: 5 Cardiometabolic Anchors

    Rather than offering an uncurated, broad-spectrum biomarker panel, the Thrive 5 Health Test focuses on five integrated cardiovascular, inflammatory, and metabolic indicators designed to assess cumulative chronic disease risk:

    • Apolipoprotein B (ApoB): Measures the total particle number of atherogenic lipoproteins carrying cholesterol into the artery wall, providing a more sensitive and predictive assessment of cardiovascular disease risk than standard LDL-C calculations.
    • High-Sensitivity C-Reactive Protein (hs-CRP): Assesses low-grade, systemic arterial and metabolic inflammation, a primary driver in plaque instability, metabolic dysfunction, and cardiovascular events.
    • Hemoglobin A1c (HbA1c): Reflects average blood glucose concentrations over the preceding 90 days, screening for subclinical insulin resistance, prediabetes, and type 2 diabetes progression.
    • Blood Pressure: Captures systolic and diastolic resting pressure dynamics, evaluating arterial resistance and hypertension risks.
    • Body Mass Index (BMI): Measures anthropometric baseline composition, serving as an adjunctive indicator of adiposity-related cardiometabolic strain.

    From Lab Draw to “Thrive Microsteps”

    The testing and digital engagement workflow is designed to eliminate friction between clinical lab results and daily routines. Individuals purchase the panel directly through the Labcorp OnDemand storefront and schedule blood draws at any of Labcorp’s thousands of Patient Service Centers across the United States.

    Diagnostic values, interpretive educational content, and personalized habit recommendations are delivered securely through Labcorp’s consumer portal and the MyLabcorp mobile application. Rather than issuing overwhelming lifestyle overhauls, such as generic directives to exercise 150 minutes weekly or eliminate carbohydrates, results are paired with Thrive Global’s proprietary Thrive Microsteps. These are small, science-backed behavioral changes distributed across five core lifestyle pillars: nutrition and meal timing, physical movement, sleep architecture, stress mitigation, and social connection.

    The platform also formats results into a structured clinical summary that consumers can bring directly to primary care encounters, facilitating informed discussions around preventative pharmacology, such as lipid-lowering therapies, or structured lifestyle medicine.

    “Too often, we get information about our health without guidance on what to do about it,” said Arianna Huffington, Founder and CEO of Thrive Global. “Through our collaboration with Labcorp, we are closing that gap by combining Thrive Global’s behavior change approach with lab testing for the first time. Labcorp’s scientific expertise helps people better understand what’s happening inside their bodies, and Thrive Global then helps turn that understanding into small daily habits that improve health—whether they’re managing a chronic condition or taking steps to protect their health for the future.”

    Reader Interactions

  • Peterson Health Technology Institute Report: Driving Adoption of High-Value AI in Healthcare Across Evidence, Coverage, and Payment

    Peterson Health Technology Institute Report: Driving Adoption of High-Value AI in Healthcare Across Evidence, Coverage, and Payment

    What You Should Know

    • The Peterson Health Technology Institute (PHTI) released a major national market report, titled Driving Adoption of High-Value AI in Healthcare, authored under the direction of Executive Director Caroline Pearson.
    • The report highlights that AI is fundamentally different from prior health technologies because it can perform work that previously required human labor and expertise, with the potential to expand the health system’s capacity to reach undertreated patients.
    • Formulates a critical industry warning: while artificial intelligence fundamentally differs from prior health IT by autonomously executing cognitive work previously restricted to human labor, under current fee-for-service incentives, administrative AI is accelerating broken processes, entrenching wasteful administrative friction, and driving inflationary upcoding rather than lowering total healthcare spending.

    Automating the Churn: How Fee-for-Service Warped the Algorithmic Promise

    The fundamental malfunction does not lie within the neural networks, but in the archaic financial machinery that feeds them. Because the American healthcare economy still overwhelmingly runs on fee-for-service plumbing—where hospital systems get paid for the volume and intensity of discrete transactions rather than keeping people healthy—AI is behaving exactly as free-market incentives dictate. It is automating the churn.

    Nowhere is this perversion more visible than in the quiet explosion of ambient scribing and algorithmic coding platforms. While these tools have legitimately lessened the clerical nightmare of keyboard-bound doctors, they have simultaneously handed hospitals an automated revenue pump. PHTI points to recent clinical implementations where deploying an AI scribe in ambulatory and emergency departments generated an immediate 5 percent spike in high-complexity Level 5 visits and a 7 percent jump in Level 4 encounters for established patients, putting an average of $1,004 in extra monthly billing into each doctor’s ledger. Across health networks, claims data reveals an immediate surge in billing intensity the moment an algorithm is switched on.


    The Payer-Provider Arms Race: Fighting an Automated War of Attrition

    Predictably, the nation’s health plans have not taken this lying down. Faced with what they deem aggressive algorithmic upcoding, commercial insurers have deployed their own defensive algorithms to systematically downcode, audit, and deny hospital claims before human adjusters ever see them.

    The result is a Kafkaesque, multi-billion-dollar bot war. In prior authorization—a bureaucratic gatekeeping ritual that already costs the system billions in phone calls and faxes—providers now unleash generative software to automatically compile medical necessity appeals, while payers deploy algorithmic gatekeepers to reject submissions with equal velocity. With procedure rules wildly fragmented across insurers, the automation has solved nothing. It has merely increased the speed and volume of the fighting, leaving human reviewers drowning in automated queues while patients wait in limbo for necessary care. As PHTI executive director Caroline Pearson notes, administrative AI is actively optimizing an adversarial game that drives up system-wide costs without buying a single ounce of better health.


    Starved in the Wings: The Tragic Neglect of Autonomous Chronic Care

    Meanwhile, the genuine clinical breakthroughs that could fundamentally alter the human condition remain starved of oxygen. Consider the quiet catastrophe of hypertension, an affliction that stalks nearly half of all American adults. Despite the existence of dirt-cheap, highly effective generic medications, three out of four diagnosed patients do not have their blood pressure under control because episodic, fifteen-minute doctor appointments are woefully inadequate for the titration and lifestyle coaching required to tame it.

    Clinical AI could easily crack this open. Algorithms are already capable of analyzing continuous biometric data from home cuffs, predicting individual drug responses, and adjusting doses between visits under protocol-driven guardrails. The exact same opportunity exists across behavioral health, where half the nation lives in a shortage area for mental health professionals and purpose-built conversational agents have demonstrated clinically meaningful drops in depression and anxiety.

    Yet these tools are financially suffocated because our payment rails require a human clinician’s hands and time to trigger a claim. An autonomous algorithm that monitors twenty thousand hypertensive patients and keeps them out of the cardiac intensive care unit cannot easily bill a fee-for-service code. In a system that bills for activities, an algorithm that quietly prevents an encounter generates zero revenue for a health system, while an ambient scribe that extracts an extra comorbidity code pays for itself on day thirty.


    A Blueprint for Sanity: Rewiring Incentives and Liability

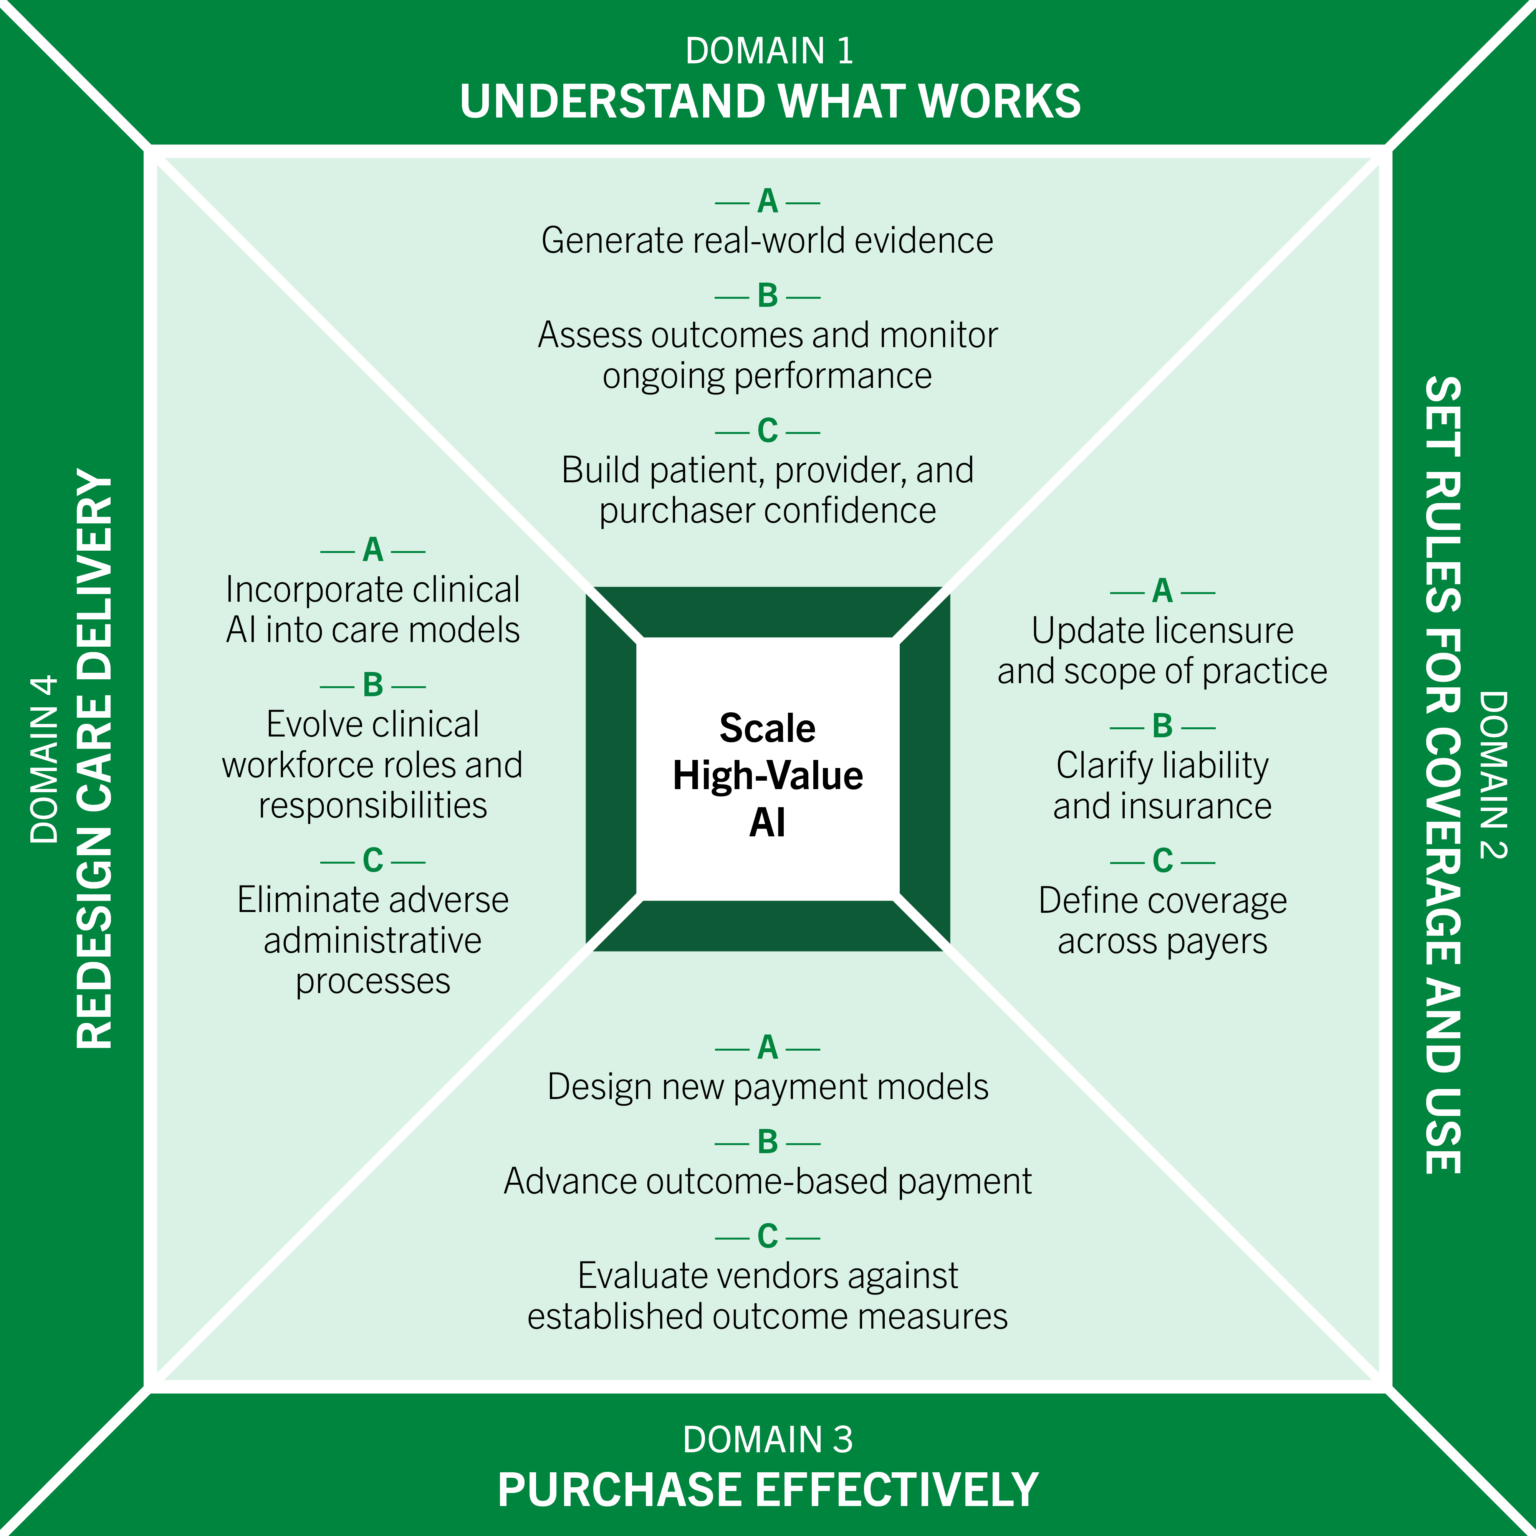
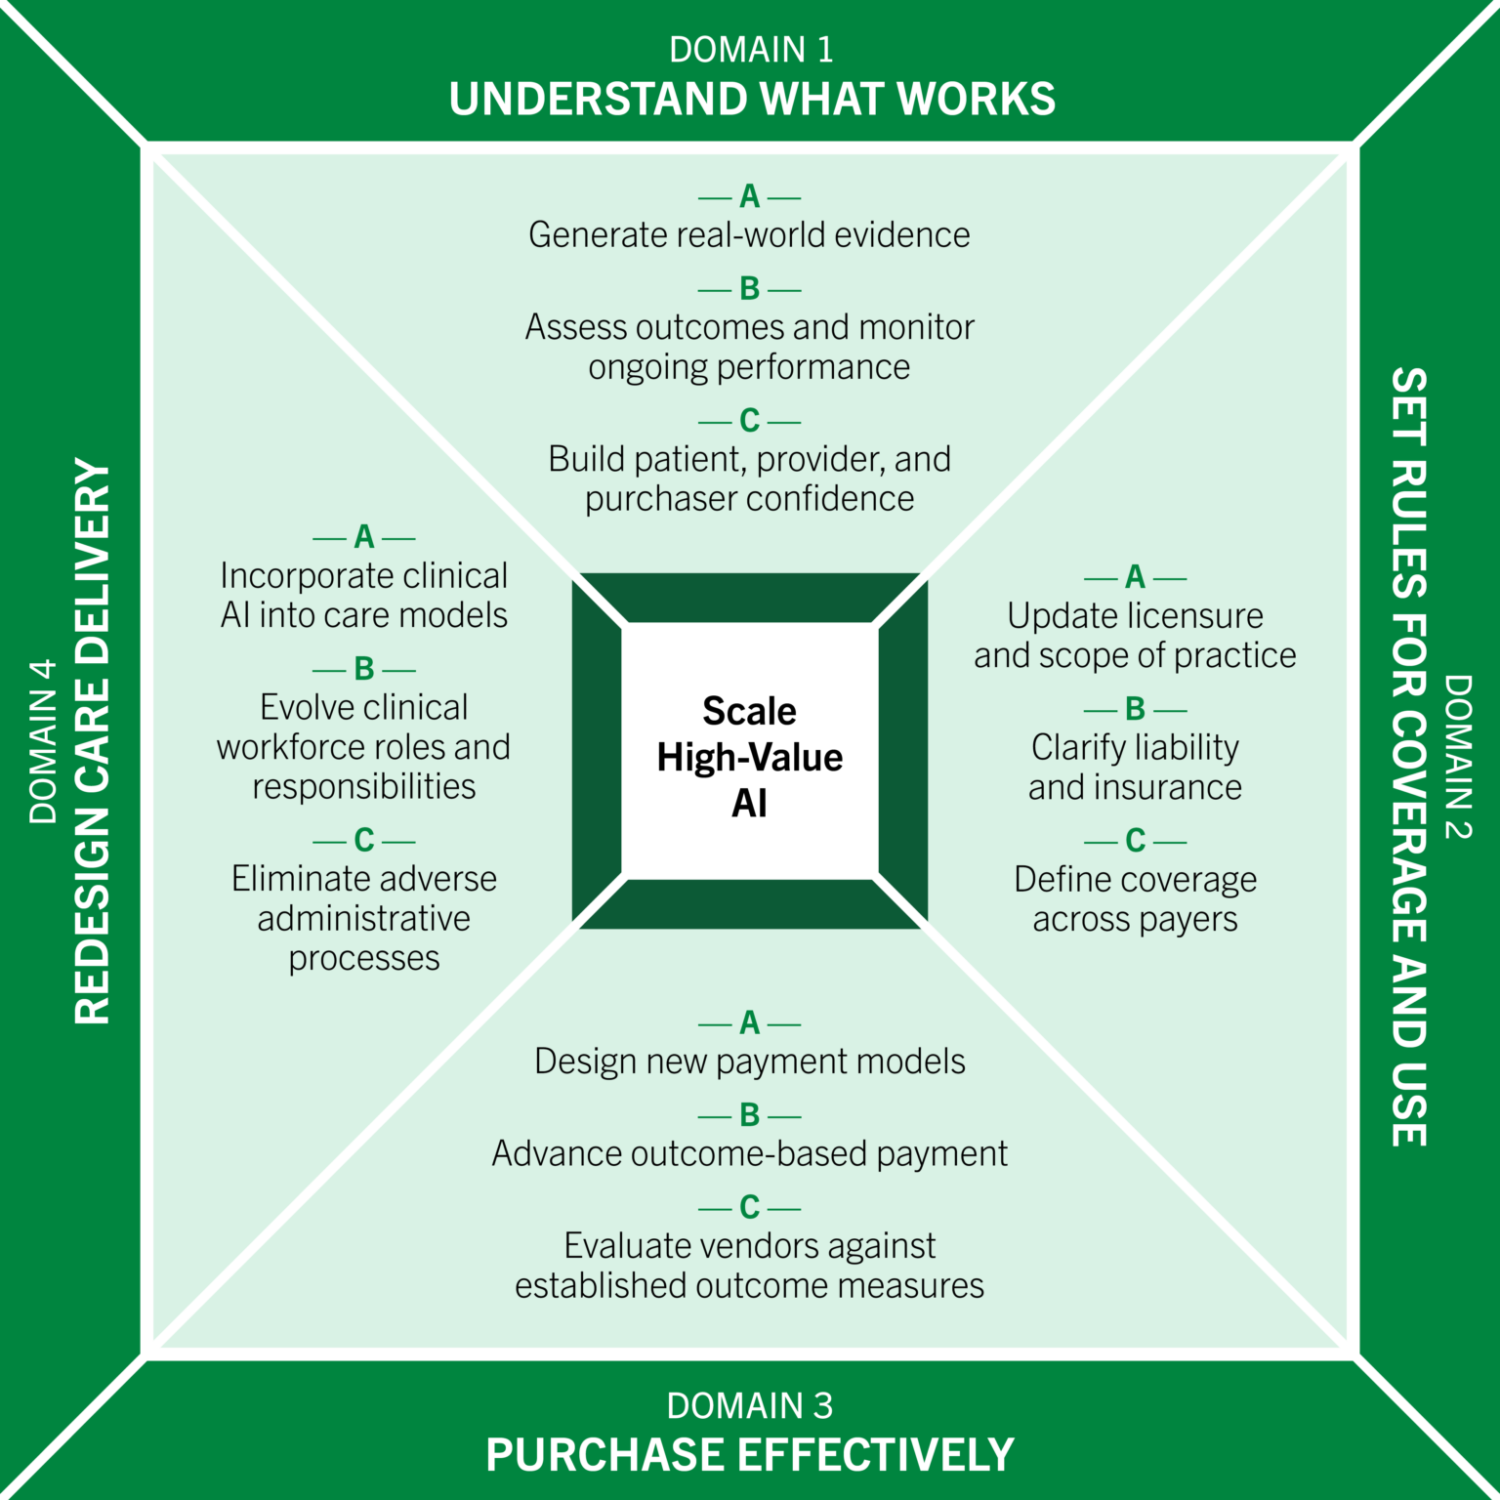
    To break this self-defeating spiral, PHTI’s blueprint—hammered out alongside hospital executives, top health plans, tech pioneers, and federal regulators at CMS, the FDA, and ARPA-H—argues that policymakers must stop treating healthcare AI like a technological problem and start treating it as a payment design problem.

    Reimbursement must decisively shift toward outcome-based payment architectures. PHTI highlights initiatives like the Center for Medicare and Medicaid Innovation’s ACCESS model, launched in mid-2026, which ties compensation to documented clinical endpoints over time rather than encounter volume. When providers are paid to achieve verified blood pressure control or depressive remission, autonomous and assistive AI suddenly becomes an indispensable cost-saving engine rather than an unbillable operational headache.

    Crucially, the report insists that payment for AI must be designed dynamically. Because software scales at near-zero marginal cost once deployed, paying standard per-use fees for clinical AI risks triggering an unprecedented wave of inflationary overutilization. Reimbursement rates should start high enough to encourage upfront clinical risk and workflow overhaul, and then ratchet downward as the software scales and unit costs collapse, ensuring the economic dividend of automation flows back to patients, employers, and taxpayers in the form of lower premiums.

    At the same time, the regulatory apparatus must catch up with reality. Medical malpractice doctrine and state licensing boards are still predicated on the fiction that an individual doctor makes every clinical choice. As initiatives like the Utah AI regulatory sandbox and the FDA’s TEMPO pilot are proving, the nation urgently needs statutory guardrails that delineate clear liability boundaries when algorithms act autonomously, shielding clinicians from unfair exposure while holding developers accountable for algorithmic drift and bias.


    “If thoughtfully deployed, clinical AI tools can close existing care gaps, extend services beyond in-person care, and improve efficiency throughout the system,” said Caroline Pearson, executive director of PHTI. “While this technology has the potential to improve patients’ health, make care more accessible and convenient, and increase affordability, we don’t currently have the systems in place to achieve that vision. We need to develop broadscale changes that enable high-value AI solutions to enter the market and to ensure that the impact and savings they produce benefit patients and families.”

  • Hospitals Can No Longer Afford to Manage Revenue Cycle After the Fact

    Hospitals Can No Longer Afford to Manage Revenue Cycle After the Fact

    Hospitals Can No Longer Afford to Manage Revenue Cycle After the Fact
    Noah Breslow, CEO, Revecore

    For years, hospital finance teams have run revenue cycle on a familiar loop: a claim goes out, a claim comes back denied or underpaid, and staff spend the next several weeks working it back. That loop was manageable when denial rates held fairly steady and reimbursement was reasonably predictable. Neither of those things is true anymore, and the gap between how revenue cycle is typically run and what today’s payer environment actually demands is widening fast.

    Denials are climbing, and they are climbing for reasons that have little to do with how hard revenue cycle teams are working. The pressure showing up in the numbers is driven by shifts in payer behavior, patient mix, and administrative complexity that no amount of appeals staffing can fully offset. A reactive model for denials is no longer enough. 

    The Reactive Model Is Running Out of Room

    The numbers make the case on their own. Kodiak Solutions, which benchmarks revenue cycle performance across more than 2,300 hospitals, found that providers on its platform lost more than $48 billion in 2025 to final denials and uncollected patient balances, a 25% increase over 2024. Clinical denials tied to prior authorization and medical necessity accounted for nearly all of that jump, and initial denial rates have now risen for five straight years.

    Experian Health’s 2025 State of Claims survey tells a similar story. Forty-one percent of providers now report denial rates above 10%, a figure that has climbed every year since the survey began in 2022, well past the 5% to 10% range HFMA considers a healthy benchmark.

    Payers have grown faster, more automated, and more willing to deny first and let providers make their case on appeal later. Reactive revenue cycle management was built for a world where denials were infrequent, and that world has disappeared.

    Complexity Is Coming From Every Direction

    Payer mix is a large part of why. Fitch Ratings expects the nonprofit hospital sector to keep shifting toward government payers as the population ages. As more claims run through Medicare and Medicaid, more of a hospital’s revenue becomes subject to rules that change frequently and get enforced unevenly across regions and plans.

    At the same time, prior authorization requirements have tightened across commercial and Medicare Advantage plans, and payers are increasingly relying on automated systems to flag claims before a human ever reviews them. Documentation gaps that used to slide through review now get caught immediately, often before a claim leaves the payer’s system.

    Increased prior authorization requirements and the shifting payer mix (including more Medicare Advantage plans) multiply the places where a claim can be delayed, denied, or underpaid. A process built to react to one denial at a time will not keep pace. 

    The Cost of Fixing Problems After They Happen

    Working a denial after the fact is costly. The American Hospital Association estimates that hospitals spent $43 billion in 2025 simply trying to collect payments insurers already owed them for care that had already been delivered. The average hospital now employs roughly 64 administrative and billing staff, about 6.5% of total hospital employment, largely to manage prior authorization, denials, and repeated documentation requests — staff time that goes toward chasing revenue that should have arrived the first time around.

    Some of that revenue never comes back at all. Claims that go unappealed or unresubmitted become permanent losses rather than delayed ones. Kodiak’s analysis of its top-performing organizations recommends directing more resources toward preventing clinical denials rather than just appealing them after the fact. That shift in orientation only works if an organization can see the patterns behind its denials rather than just the individual claims in front of it.

    What a Proactive Revenue Cycle Actually Looks Like

    Proactive revenue cycle management starts when you look at patterns of claim denials vs. the individual claims themselves. That requires analyzing denials and underpayments at the root cause level, tracing a problem back to the payer, the service line, the documentation gap, or the workflow step that keeps generating it, and fixing that step before claims go out the door instead of fighting each one after it comes back.

    Most revenue cycle teams were not built to operate this way. Treating denial and underpayment data as a feedback loop into clinical documentation, coding, scheduling, and patient access is a different discipline than working a queue of appeals, and it gives finance leaders visibility into where revenue is at risk before it turns into a write-off, rather than after. It also changes what success looks like. Recovered revenue still matters, but the number worth watching more closely is how much denial volume never happens in the first place.

    Revenue Cycle Belongs in the Strategic Conversation

    Hospital leaders can control how quickly their organization identifies the root cause of a reimbursement problem and closes it, regardless of demographic shifts, payer mix, or how aggressively insurers adjudicate claims. With costs rising and margins remaining thin across much of the sector, that capability may be the difference between a hospital making or losing money. Health systems that rapidly detect denial patterns and address root causes through operational improvements are the ones most likely to protect their margins over the next several years. These organizations will hold their footing while others spend the next few years chasing revenue they should have collected the first time.


    About Noah Breslow

    As CEO of Revecore, Noah Breslow brings more than 20 years of executive leadership experience, with a focus on driving growth, innovation, and transformation in complex, highly regulated industries. Most recently, Breslow was a Partner at Bain Capital Ventures (BCV), where he led their portfolio support team, built out data-driven investment tooling, and helped incubate two startups at the forefront of applying AI in the insurance claims processing and wealth management industries.

    Prior to BCV, Breslow served as Chairman and CEO of OnDeck, a pioneering online small business lender, where he built the business from its earliest stages, took it public and ultimately facilitated its acquisition. OnDeck used data and analytics to effectively deliver capital at scale to businesses historically underserved by banks. Earlier in his career, Breslow held leadership roles in product, engineering and marketing. He holds a Bachelor of Science in Computer Science and Engineering from MIT and an MBA from Harvard Business School.


  • Pharma’s Billion-Dollar AI Bets May Be Chasing the Wrong Advantage

    Pharma’s Billion-Dollar AI Bets May Be Chasing the Wrong Advantage

    Pharma's Billion-Dollar AI Bets May Be Chasing the Wrong Advantage
    Shashi Shankar, Co-Founder and CEO, Novellia

    2026 will be remembered as the year pharma went all in on AI.

    Since January, nearly every major pharmaceutical company has announced some version of the same thing. GSK signed a five-year foundation-model deal with Noetik. Eli Lilly built a co-innovation lab with NVIDIA. Merck committed a billion dollars to Google Cloud. This month, Novo Nordisk named Amazon Web Services its preferred AI partner. The dollar figures are staggering. And the messaging has been almost identical across all of them: get access to the right model, the right compute, the right discovery platform, and you’ll win the next decade of drug development.

    Then Q2 earnings calls wrapped, and almost no one could point to a measurable return. A faster trial. A failure caught earlier. A drug that reached folks sooner because of what they’d invested. Executives talked about pilots and roadmaps. The announcements are loud but the silence on results is the real story.

    I get why these deals get announced the way they do. The models are really incredible. But when everyone has access to roughly the same model capability, the model stops being an advantage. It becomes table stakes, like electricity. Nobody wins on having electricity. They win on what they build with it.

    A lot of the conversation this year has moved toward the discovery platform or the algorithm on top of the model as the real differentiator. That’s closer. But I’d push it one level further. The real edge is the data the platform is trained and run on. A world-class algorithm trained on incomplete, fragmented, clinically thin data will still give you incomplete, fragmented, thin answers. That’s the layer none of these mega-deals have actually touched.

    To understand why, think about what it actually looks like when a real person tries to navigate serious illness in this country.

    Take someone managing a rare condition who sees six different specialists over four years. Her rheumatologist is in one system. Her neurologist is in another. Two of her earlier records exist at  community clinics she stopped going to. By the time anyone tries to assemble a complete picture of what’s happened to her, half the story is missing or inaccessible. And she’s one of the simpler cases.

    The US has no unique patient identifier. Providers have little regulatory incentive to share records across systems. A single person’s health history can be scattered across every hospital, lab, specialist, and health system they’ve ever seen. Insurance coverage varies by state and plan. Hospitals and their clinics inside the same health system often run on different EHR platforms that don’t talk to each other. Nobody has a complete picture of the folks these drugs are actually designed to serve.

    Claims-based real-world data, the first data type I ever worked with as an intern at Genentech well over a decade ago, are still the primary input for most pharma real-world evidence work and inherit all of that fragmentation. Claims were designed for billing. They can tell you a treatment happened. They can’t tell you what led to it or why. The clinical context lives in physician notes, which are unstructured, inconsistent, and scattered across decades of care. Basic social factors like housing, income, and smoking status are frequently missing. Seventy-eight percent of health organizations say they can’t even locate social-determinant data in a patient’s record after it’s been collected.

    Clinical trials are rigorous by design, and that rigor is also what limits them. They’re built around selected populations, defined observation windows, and specific endpoints. A person enrolled in a six-month trial doesn’t stop being a patient after month six. They get new conditions. They switch doctors. They move. With many rare diseases, patients might see seven different physicians before anyone lands on the right diagnosis. None of that shows up in a trial dataset. Most of it doesn’t show up cleanly in claims either.

    The folks who are hardest to capture accurately in current datasets are usually the people a drug needs to work for the most. Complex conditions. Multiple diagnoses. Long, difficult care journeys. That’s where the data falls shortest, and that’s where the AI answers will be weakest.

    I spent over a decade inside biopharma. I watched incredibly talented teams work hard with an incomplete picture of the people they were trying to help. That gap was always there. What’s new is the scale of investment now being built on top of it.

    The next real competitive edge in this industry will come from the less glamorous work of actually fixing the data. Connecting fragmented records. Capturing the clinical detail sitting in unstructured notes. Building datasets that reflect the full reality of the folks who will rely on a new medicine to save their lives, including the ones that don’t fit neatly into a trial population.

    That work is harder to announce. It doesn’t generate the same headlines. It’s also what determines whether these AI investments eventually deliver.

    The only thread that runs through every part of the care journey is the patient. Every physician visit, every lab, every specialist, every prescription. When you stitch the data around that reality, with the patient’s knowledge and consent, the fragmentation starts to resolve itself. That’s a fundamentally different starting point than what most of the industry is working from today.

    There are real people on the other side of this. A father whose daughter just got a life-changing diagnosis that should have come four years earlier, and has to reckon with what those four years might have cost her. A family sitting in a waiting room, wondering whether the new drug their mom just started is actually working. These are the people whose care journeys are scattered across systems. Getting the data piece right is how the industry actually reaches them, in time, with the right answer.

    About Shashi Shankar

    Shashi Shankar is Co-Founder and CEO of Novellia. He spent over a decade at Genentech and Roche in medical affairs, health economics, and digital health innovation.


  • STAT+: The startup chasing ‘general biological intelligence’

    STAT+: The startup chasing ‘general biological intelligence’

    Brittany Trang, Ph.D., covers AI in health and medicine: Does it actually work? Who benefits, or might be harmed? She writes the weekly AI Prognosis newsletter. Follow her on Threads, Mastodon, and Bluesky. You can reach Brittany on Signal at btrang.01.

    This is the web edition of STAT’s AI Prognosis newsletter, our guide to artificial intelligence in health care and medicine. Sign up to get it delivered in your inbox every Wednesday. 

    Today is the first day of the STAT Summit in Boston! If you’re not attending in person (tickets for tomorrow are still available!), you can tune in virtually. Subscribers get a 40% discount on both virtual and in-person tickets.

    I’m looking forward to “When the Promise of AI Doesn’t Pan Out,” which is scheduled for just after noon ET today, and STAT executive editor Rick Berke’s interview with Katelyn Jetelina, better known as “Your Local Epidemiologist,” whom I’m still starstruck by. 

    STAT+ Exclusive Story

    Already have an account? Log in

    STAT+

    STAT+

    This article is exclusive to STAT+ subscribers

    Unlock this article — plus in-depth analysis, newsletters, premium events, and news alerts.

    Already have an account? Log in

    View All Plans

    To read the rest of this story subscribe to STAT+.

    Subscribe

  • FDA Launches Rare Disease Framework Initiative to Modernize Small-Cohort Trial Design

    FDA Launches Rare Disease Framework Initiative to Modernize Small-Cohort Trial Design

    FDA Announces Real-Time Clinical Trial Pilot Program and Proof-of-Concept Studies with AstraZeneca and Amgen

    What You Should Know

    • The U.S. Food and Drug Administration (FDA), an operating division of the U.S. Department of Health and Human Services (HHS), officially announced the launch of the Rare Disease Framework Initiative.
    • Accompanied by the publication of a new agency white paper outlining a “fit-for-purpose” regulatory model engineered to match trial requirements to the realistic evidentiary constraints of ultra-small, geographically dispersed patient populations.
    • Addresses a critical clinical deficit across orphan therapeutics: although an estimated 7,000 to 10,000 distinct rare diseases affect more than 30 million Americans, only approximately 5% currently possess an FDA-approved treatment.
    • The initiative is coordinated across agency divisions by the FDA’s Rare Disease Innovation Hub, operating in formal partnership with the Office of the Commissioner, the Center for Drug Evaluation and Research (CDER), and the Center for Biologics Evaluation and Research (CBER).

    The Five Percent Dilemma

    The initiative comes at a critical inflection point for biotechnology. Over four decades since the passage of the landmark Orphan Drug Act of 1983, regulatory flexibility and market incentives have spurred life-saving gene therapies, enzyme replacements, and targeted biologics. Yet the sheer scale of unmet medical need remains staggering: roughly 95 percent of all identified rare conditions still lack a single FDA-approved therapy.

    For families navigating ultra-rare genetic mutations, the agonizingly slow pace of drug development is compounded by regulatory unpredictability. Promising therapies often stall during late-stage reviews when sponsors struggle to demonstrate statistical significance using conventional clinical endpoints, or when chemistry, manufacturing, and controls requirements designed for mass-market pills prove ill-suited to custom, patient-derived cell therapies.

    The FDA’s new framework seeks to realign that process with the statistical realities of micro-populations. Under the initiative, the agency will evaluate therapeutics through customized evidentiary lenses, factoring in the biological nuances of each disease, the natural history of progression, and novel Bayesian trial designs that can extract statistically valid efficacy signals from just a handful of trial participants.

    A New Architecture at White Oak

    Central to the rollout is the newly established Rare Disease Innovation Hub, a cross-cutting regulatory entity designed to break down bureaucratic silos across the FDA’s two primary review divisions: the Center for Drug Evaluation and Research (CDER) and the Center for Biologics Evaluation and Research (CBER).

    Historically, developers targeting the same rare disorder with different therapeutic modalities—such as a small-molecule drug handled by CDER versus an adeno-associated virus gene therapy overseen by CBER—could face drastically divergent evidentiary demands and conflicting reviewer cultures. The Hub, directed by rare disease veteran Amy Comstock Rick, will serve as a single point of operational alignment, ensuring sponsors receive consistent guidance regardless of whether their product is a pill, an antibody, or an individualized genetic edit.

    Agency leadership signaled that the transformation will reach beyond clinical trials into manufacturing and post-market surveillance. The agency has committed to applying risk-based models to pre-approval inspections and chemistry standards, preventing regulatory bottlenecks from indefinitely delaying life-saving batches of customized treatments. In parallel, the framework plans to formalize patient and caregiver testimony directly into milestone review meetings, treating lived experience as structured qualitative data rather than a ceremonial addendum.

    A Crucible for the Future of Medicine

    To begin shaping the detailed regulations, revised guidances, and internal reviewer training modules, the FDA will convene a major public stakeholder summit on October 28 at its White Oak headquarters in Silver Spring, Maryland, facilitated by the Reagan-Udall Foundation. The hearing will bring together patient advocacy coalitions, academic geneticists, venture-backed biotechnology executives, and federal reviewers for the first of several sector-specific roundtables.

    Reader Interactions

  • Verily Health Awarded CDC Contract for National Wastewater Surveillance System: Scaling Genomic and Metagenomic Public Health Analytics

    Verily Health Awarded CDC Contract for National Wastewater Surveillance System: Scaling Genomic and Metagenomic Public Health Analytics

    Verily and Vanderbilt Extend Partnership to Power NIH's All of Us Researcher Workbench

    What You Should Know

    • Healthcare data intelligence leader Verily Health Inc. has been awarded a multi-year contract renewal by the Centers for Disease Control and Prevention (CDC) to continue operating and expanding the National Wastewater Surveillance System (NWSS).
    • Builds on a four-year operational foundation: the contract extension expands the public health surveillance partnership Verily has maintained with the CDC since 2023.
    • Delivered through Verily Sightline, the company’s specialized public health platform that unifies wastewater epidemiology, high-throughput molecular laboratory testing, bioinformatic data analytics, and software infrastructure to monitor population-level infectious disease transmission trends.
    • Introduces advanced genomic capabilities: the expanded CDC program will support continuous pathogen detection, targeted viral and bacterial genomic sequencing, and the incorporation of potential metagenomic surveillance capabilities to detect novel and emerging pathogens before they appear in clinical settings.

    Core Program Architecture: Verily Sightline & Expanded Metagenomics

    Under the renewed CDC mandate, Verily combines physical laboratory pipelines with population-level health informatics to track infectious disease dynamics:

    • End-to-End Operational Pipeline: Verily Sightline integrates sample intake from municipal wastewater treatment facilities, high-throughput biospecimen processing, quantitative PCR assays, and automated cloud data pipelines that feed actionable epidemiological intelligence directly into CDC reporting dashboards.
    • Pathogen-Specific Assays: Continues routine monitoring for established respiratory and gastrointestinal pathogens, including SARS-CoV-2, Influenza A/B, and Respiratory Syncytial Virus (RSV), alongside flexible surge testing for emerging zoonotic threats such as avian influenza (H5N1).
    • Genomic Sequencing & Variant Tracking: Performs high-density genomic sequencing to track lineage mutations, detect novel viral variants, and monitor antimicrobial resistance (AMR) markers before they appear in clinical hospital isolates.
    • Metagenomic Surveillance Expansion: Integrates prospective metagenomic next-generation sequencing (mNGS) capabilities. Metagenomic testing analyzes total genetic material in a wastewater sample without requiring pre-designed targeted primers, equipping public health officials with an unbiased discovery tool to identify previously uncharacterized or novel biological threats.

    “We’re proud to continue our work with the CDC on a program that strengthens national public health surveillance,” said Stephen Gillett, Chairman and CEO of Verily Health. “At Verily Health, we are building the data foundation for the future of healthcare intelligence, bringing together complex health data, scientific expertise, and advanced analytics to generate actionable insights that accelerate research and improve healthcare.”

    Reader Interactions

  • STAT+: Lobbyists and trade groups fight to shape how states regulate medical AI

    STAT+: Lobbyists and trade groups fight to shape how states regulate medical AI

    Influential lobbying groups for doctors and hospitals, a health insurer, technology companies, and representatives from state governments met behind closed doors in Washington, D.C., in early October to develop guidelines for how to regulate artificial intelligence in the practice of medicine.

    Executives from the American Medical Association, American Hospital Association, artificial intelligence giant Anthropic, and insurer Elevance Health are part of a 22 member AI workgroup convened by the Federation of State Medical Boards, or FSMB, a national organization that advocates for state boards. A spokesman said the workgroup “was built to balance expertise across medical regulation, AI development, care delivery, academic medicine, state AI policy, and patient safety,” and that its recommendations would be open for feedback before being formally adopted.

    The discussions within workgroup meetings are being kept confidential, but the goal is to draft guidelines to aid local medical boards, with “particular attention … to AI tools that perform clinical functions with limited or no direct physician supervision,” Humayun Chaudhry, the FSMB’s president and CEO, told STAT. A draft of the recommendations could be made public in “weeks to months,” said Chaudhry. They could ultimately form the basis of legislation in states, which individually regulate medical licensure and the practice of medicine.

    STAT+ Exclusive Story

    Already have an account? Log in

    STAT+

    STAT+

    This article is exclusive to STAT+ subscribers

    Unlock this article — and get additional analysis of the technologies disrupting health care — by subscribing to STAT+.

    Already have an account? Log in

    View All Plans

    To read the rest of this story subscribe to STAT+.

    Subscribe