The company says it will use the money to develop AI agents and deepen its relationships with its 30 health technology partners.

The company says it will use the money to develop AI agents and deepen its relationships with its 30 health technology partners.


Assembling the Full Pathology Stack
By acquiring Proscia, Agilent secures the missing software operating system. Instead of selling discrete instruments and reagents, Agilent can now deliver an end-to-end ecosystem: tissue preparation reagents, automated staining instrumentation, vendor-neutral whole-slide ingestion, and regulatory-cleared diagnostic software.
Agilent and Proscia originally entered into a multi-year global distribution agreement in September 2022 to co-develop and sell integrated diagnostic pathology workflows. Acquiring Proscia transitions an external commercial alliance into an owned intellectual property core.
Agilent is a primary diagnostic partner for global pharma, co-developing FDA-approved companion diagnostic tests that determine patient eligibility for targeted cancer immunotherapies. Integrating Concentriq gives Agilent a direct digital data conduit into 16 of the top 20 biopharmas, creating an R&D feedback loop that unites prospective biomarker discovery with downstream clinical commercialization.
The acquisition brings a high-margin, recurring-revenue software foundation into Agilent’s diagnostic portfolio:
“Digital pathology is quickly becoming the foundation for pathology data generation, analysis, and application across biopharmaceutical research, clinical development, and diagnostics, and our acquisition of Proscia meaningfully expands our presence in this fast-growing market,” said Padraig McDonnell, President and CEO of Agilent. “The acquisition establishes an Agilent platform for scientific intelligence in tissue-based precision medicine, connecting data generation with AI-based interpretation in a workflow that supports biomarker research through routine clinical use. With Proscia’s leading platform and talented team, we will be better equipped to help laboratories and biopharma customers manage and derive insights from pathology data.”


CortexLM transitions clinical chart auditing from retrospective damage control to proactive, pre-submission revenue integrity. Rather than relying on random statistical spot-checks, CortexLM reads and analyzes 100% of individual patient notes across a practice. The model evaluates chart documentation against specialty-specific clinical practice parameters, individual commercial payer medical policies, CMS billing regulations, and quality reporting criteria.
By operating prior to billing, the system identifies diagnostic inconsistencies, missing documentation components, coding gaps, and non-compliant phrasing before claims are submitted to clearinghouses or payers. CortexLM then proposes specific clinical documentation fixes to treating providers while encounters are fresh. In addition to mitigating clawback exposure, the system audits for legitimate clinical complexity and documentation integrity, uncovering billable services and comorbidities that providers delivered but omitted from final claim drops.
Brellium has achieved national enterprise penetration across multi-specialty medical groups, home health systems, and high-volume behavioral health networks. The platform is currently trusted by more than 215,000 clinicians across 200 provider groups operating in all 50 U.S. states. To date, Brellium has processed and audited more than 22 million patient visits, protecting nearly $2 billion in provider revenue from post-payment recoupments, payer clawbacks, and audit penalties.
Enterprise customers include national home health and post-acute providers Gentiva and Maxim Healthcare, as well as scaled behavioral health networks Headspace and Rula. At Headspace, adopting Brellium enabled the organization to scale its clinical quality assurance coverage from auditing two percent of therapy notes to 100%, driving provider compliance with clinical documentation standards to 99.2%.
The Brellium Audit Guarantee
The defining commercial innovation of Brellium’s model is its financial guarantee. If CMS, a Medicare Administrative Contractor, or a private commercial health plan audits a chart and issues a financial clawback or penalty on a visit that Brellium previously reviewed and cleared, Brellium foots the bill instead of the provider.
This structure directly tackles the primary liability barrier identified in the Bessemer and Bain 2026 Healthcare AI ROI Scorecard, which noted that clinicians and provider organizations routinely avoid scaling AI because they bear full medico-legal and financial liability for algorithmic outputs. By putting its own balance sheet behind its algorithmic auditing engine, Brellium removes the liability defense used by risk-averse CFOs and compliance committees, elevating its software from a passive documentation tool to an insurable standard of truth.
The $23M capital raise will be deployed to broaden clinical coverage and deepen billing integration. Brellium is scaling beyond its foundational footprint in behavioral health and home care into high-complexity, high-dollar specialties heavily targeted by Recovery Audit Contractors, including cardiology, interventional pain management, and value-based primary care.
Operationally, the company is deepening bi-directional integrations with practice management and EHR billing engines to automate coding validation, modifier application, and pre-claim clearinghouse handoffs. Brellium is also expanding conversations with health plans to position CortexLM as a shared, objective pre-payment validation layer, enabling auto-adjudication and clean-claim passes that eliminate post-payment audit friction entirely.
“Providers and payers have been stuck fighting the same fraud, waste and abuse problem from opposite sides of the table for years,” said Zach Rosen, Co-Founder and CEO of Brellium. “CortexLM is how we get everyone working from the same standard, so providers can prove the care was right the first time, instead of spending months untangling it after the fact.”


Connecting Mandates to Operational Follow-Through
Readily operates as a centralized regulatory intelligence layer, bridging the divide between external regulatory text and internal operational execution. Readily scans and parses federal registers, state administrative updates, and Medicaid plan letters in real time, automatically mapping statutory changes to affected internal policies, member benefit grids, and vendor contracts.
Key features include:
Automated Redlining and Policy Drafting: Generates redlined policy revisions and updated procedure language that align with newly enacted rules, reducing manual legal and policy review cycles from weeks to minutes.
Workflow Accountability & Task Orchestration: Assigns operational updates directly to business unit owners (e.g., claims configuration, utilization management, network contracting) and tracks completion status across teams, eliminating blind spots where policy changes fail to reach frontline workflows.
Continuous Audit Evidence Compilation: Automatically aggregates required universes, correlates operational actions with statutory requirements, and compiles auditable evidence packages—allowing health plans to defend their compliance posture during CMS or state audits in seconds rather than spending months retrieving files.
Human-in-the-Loop Governance: Keeps qualified compliance, operational, and legal leaders accountable for final sign-off, ensuring that algorithmic analysis augments human oversight without displacing professional legal judgment.
Readily has achieved rapid enterprise penetration across the U.S. managed care ecosystem:



Jason is a general assignment reporter, with particular focus on genetic medicine and rare disease. Confidential tips can be sent on Signal at JasonMast.77.
Martin Shkreli is back. The Federal Trade Commission isn’t happy.
The FTC and seven states on Tuesday asked a federal court to hold Shkreli in contempt for “flagrantly and repeatedly” violating a court order banning him from working in the pharmaceutical industry.
Shkreli, who became known nationwide as “pharma bro” in the 2010s for imperiously defending his decision to raise the price of an anti-parasitic drug called daraprim by 5,000%, was sentenced to seven years in prison for defrauding investors in 2018. Before he was released in 2022, a court banned him from ever working in the drug industry again, saying he illegally tried to prevent generic competition to daraprim.
STAT+ Exclusive Story
Already have an account? Log in


Already have an account? Log in
To read the rest of this story subscribe to STAT+.

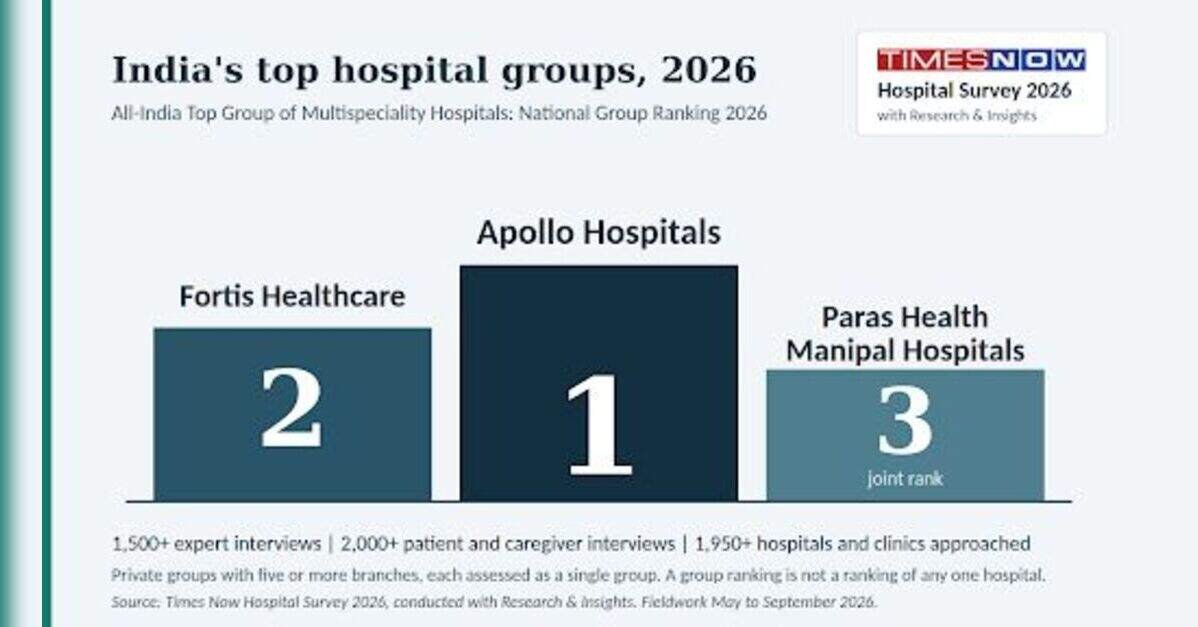
New Delhi, October 2026: Apollo Hospitals has secured the first position and Fortis Healthcare the second in the All-India Top Group of Multispeciality Hospitals – National Group Ranking 2026, conducted as part of the Times Now Hospital Survey 2026. Manipal Hospitals and Paras Health have jointly secured third place, bringing together four healthcare groups that represent different approaches to building and expanding multispeciality care in India.
Conducted by Times Now in association with research partner Research & Insights, the survey assessed private hospital groups as integrated healthcare networks rather than evaluating individual hospitals in isolation. The first results draw attention to a question facing India’s healthcare sector: how effectively can hospital groups maintain clinical capabilities, infrastructure and patient-care standards across multiple locations?
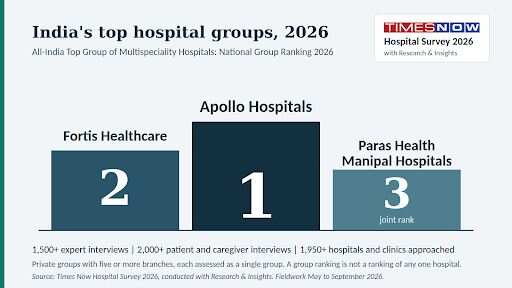
Source: Times Now Hospital Survey 2026, National Group Ranking.
The survey was conducted between May and September 2026. Its methodology combined desk research, more than 1,500 interviews with doctors and medical specialists, more than 2,000 interviews with patients and caregivers, and fact sheets sent to more than 1,950 hospitals and clinics. The assessment combined expert and patient perceptions with factual information on clinical quality, infrastructure, human resources, accreditation, patient safety, and academic and research capability.
Only private hospital groups with at least five operational branches were eligible. Government, partly government-funded, charitable and not-for-profit hospitals were excluded. The results reflect each eligible group as a single entity and should not be read as rankings of individual campuses. The survey also allows the same rank where the statistical gap between two entities is very small, as in the joint third place.
Figures in this section are as published by the groups on their own websites in October 2026.
Apollo Hospitals, which secured the first position, says it opened India’s first corporate hospital in 1983 and has since built a broad healthcare ecosystem spanning hospitals, pharmacies, diagnostics and primary-care clinics. The group reports more than 10,000 beds and a pharmacy network of over 4,000 outlets. Its scale reflects how organised private healthcare has moved from individual institutions to interconnected networks.
Fortis Healthcare, ranked second, reports 36 healthcare facilities across 12 states, with more than 6,000 operational beds, spanning hospitals, diagnostics and day-care specialty facilities. Its stated mission centres on clinical excellence and patient care.
Manipal Hospitals, which shares third place, traces its roots to the founding of Kasturba Medical College in 1953, with its first hospital opening in Bengaluru in 1991. The group reports 49 hospitals in more than 24 cities and over 12,600 beds, and says its network is expanding across metro and tier-II cities.
Paras Health’s joint third place brings a different dimension to the ranking: the development of advanced multispeciality care in markets where specialised treatment has often been harder to find close to home.
While much of India’s organised private healthcare infrastructure has historically been concentrated in the major metros, Paras Health has built a network across northern and eastern India, largely in cities beyond the largest metropolitan centres. Its eight hospitals are in Gurugram and Panchkula in Haryana, Patna and Darbhanga in Bihar, Ranchi in Jharkhand, Udaipur in Rajasthan, Kanpur in Uttar Pradesh and Srinagar in Jammu & Kashmir, a presence in five states and one Union Territory.
According to its website, Paras Health describes itself as having 20 years in healthcare, has treated more than 2.1 million patients across multiple states, and has a team of more than 2,100 doctors and nurses. Its clinical services include cardiac sciences, oncology, neurosciences, gastro sciences, orthopaedics, renal sciences, and liver transplant and GI surgery, among other specialties. The group’s Srinagar hospital marked three years in May 2026.
Building a multispeciality hospital outside an established metropolitan hub takes more than physical infrastructure. Hospitals must attract and retain experienced clinicians, establish multidisciplinary teams, invest in specialised equipment, maintain quality and patient-safety systems, and develop the operational capability to support complex treatments.
These requirements can be harder to meet in Tier-II and Tier-III markets, where specialised clinical talent, supporting medical infrastructure and referral networks may differ from those in larger cities, and where providers must balance affordability against the cost of advanced services. For patients, having such services locally can reduce the need to travel to metropolitan centres for consultations, diagnostics and treatment.
Paras Health’s presence in Patna, Darbhanga, Ranchi, Kanpur, Udaipur and Srinagar illustrates an emphasis on building this capacity outside the largest markets. Manipal’s presence across metro and tier-II markets shows how established national networks are also broadening their reach. The two approaches differ in scale and geography, but both point to the growing importance of extending organised healthcare beyond traditional urban centres.
The challenge is not simply to open hospitals in more cities, but to sustain clinical capability, patient experience and quality systems across an entire network. The Times Now survey assesses groups against that institutional perspective. However, the published ranking does not provide criterion-wise scores showing that any single strategy or factor determined a group’s position. Paras Health’s joint third place should therefore be read as a national group-level outcome, with its expansion model an illustration of the wider shift towards advanced care in non-metropolitan India.
The first release of the Times Now Hospital Survey 2026 places Apollo Hospitals, Fortis Healthcare, Manipal Hospitals and Paras Health within the national conversation on organised multispeciality healthcare. Their positions bring different network models into focus, from the scale of established national chains to the development of advanced care in markets beyond the largest cities. As hospital networks continue to expand, the ability to sustain clinical capability across locations will remain an important consideration for patients, healthcare professionals and the wider industry.
The survey’s campus-level, specialty, zonal and city-level results, being released in stages, are expected to add further perspective on individual hospitals and healthcare markets.
About the survey: The Times Now Hospital Survey 2026 was conducted by Times Now in association with Research & Insights. It assesses eligible private hospitals and hospital groups through desk research, medical-expert interviews, patient and caregiver interviews, and factual hospital data. Results are being released in stages across national group, hospital, specialty, zonal and city categories.
A note on the figures: Network figures for Apollo Hospitals, Fortis Healthcare, Manipal Hospitals and Paras Health are as published on each group’s website in October 2026 and may change. Survey details are from the Times Now Hospital Survey 2026 methodology.
Disclaimer: The above content is non-editorial, and TIL hereby disclaims any and all warranties, expressed or implied, relating to it, and does not guarantee, vouch for or necessarily endorse any of the content.


As a rheumatologist, I treat rheumatoid arthritis (RA) and other complex autoimmune diseases. If you have or happen to develop one of these diseases, I am thankful that science has delivered amazingly effective targeted therapeutics and biologics in recent decades. While highly effective, these treatments come with a high economic cost, so I have grown accustomed to daily battles with commercial insurance plans to get working-age patients the treatments they need. While horror stories abound regarding commercial insurers, Medicare has traditionally been a more predictable partner for my older patients. Medicare reimbursement is low — an issue worthy of a separate commentary piece — but comes on time, typically without the hassle and administrative delays of prior authorizations, assuming we use our therapeutics within FDA-approved dosing and indications.
On top of these existing challenges here in the Midwest, providers recently won a battle we did not expect to have to fight with a Medicare administrative contractor (MAC). The story deserves scrutiny from legislators and regulators nationwide.
Medicare beneficiaries rightly assume, as have I, that policy spells out the services they are entitled to receive. Lawmakers in Congress establish patients’ benefits in law, while the Centers for Medicare & Medicaid Services (CMS) develops the national rules and policies to implement them. MACs fit into this process by administering those rules regionally (with some discretion), but they are not supposed to privately create new substantive conditions of payment.
Recently, the MAC overseeing Kentucky and Ohio began auditing and denying claims for intravenous Orencia, a biologic drug used to treat RA, citing a “lack of medical necessity.” The policy affected more than a hundred patients who had mostly been on Orencia for a decade or more. These patients were forced to stop or delay treatment or switch therapies, which resulted in serious RA flares. MAC administrators had decided that most patients on intravenous Orencia, covered under Medicare Part B, should instead receive subcutaneous Orencia, covered under Medicare Part D and often at substantially higher out-of-pocket cost.
The decision was made without a formal notice-and-comment process. In fact, this requirement does not even appear in the Medicare guidance cited for this decision. Worst of all, it effectively forced dozens of patients off a life-changing therapy.
Thanks to outreach from clinicians, national advocacy organizations, angry patients, and congressional representatives, this policy was walked back. Or at least, we think so. There was no announcement of a reversal. Instead, the MAC covering Kentucky and Ohio quietly revised a fact sheet on its website, removing language that preferred subcutaneous over intravenous dosing.
This whiplash has been devastating to my own small clinic, however, as the MAC continues to withhold the equivalent of roughly three payrolls’ worth of payments for treatments we rendered in good faith during this period. They have also not answered repeated inquiries about whether denials issued under the now-removed standard will be reversed.
This situation exposed several problems that need to be addressed before this happens to other MACs, Medicare beneficiaries and clinicians:
1. The current system allowed one medical director’s opinion to acquire the force of Medicare policy without an effective check. This violates the Supreme Court’s decision in Azar v. Allina, which limits the government’s ability to create substantive Medicare payment standards through informal guidance. Yet it still took months of work, worry, and countless hours distracted from providing clinical care to get the issue elevated to a level where the policy was reconsidered.
2. There is inadequate accountability and little transparency within MAC operations. After an initial call with the MAC medical director to raise this issue, we went for weeks with response and no clue as to where our appeal stood. Providers didn’t know how to “correctly” care for our affected patients. When the disputed language did quietly disappear from the fact sheet, there was no public explanation, formal announcement, or directive regarding claims already denied.
3. There is no clearly identified chain of command to move a critical issue of patient harm from a regional MAC to CMS. As an experienced advocate, I leveraged my relationship with my congressional representative and the American College of Rheumatology to elevate this issue to CMS, but what if I hadn’t had those relationships? Our system should not require physicians to become experts in Medicare law and policy just to ensure the Medicare system follows its own rules.
Medicare beneficiaries deserve better. While in this case we’ve been able to protect access to intravenous Orencia, this experience exposed flaws that extend far beyond one drug or one MAC contractor. We should all be concerned that MACs are increasingly making unilateral decisions that negatively impact patient access. Medicare policy should be transparent and include appropriate notice and stakeholder input. And when a contractor gets it wrong, there should be a clear and rapid way to stop the harm to patients, their relationship with their doctor and the doctor’s practice. A patient’s access to Medicare-covered care should never depend on whether their physician can find someone in Washington willing to intervene. Something must change.
Author bio:
Dr. Chris Phillips is an American College of Rheumatology leading rheumatologist and owner of Paducah Rheumatology.
Photo: Stas_V, Getty Images


The lawsuit isn’t a surprise, after Alignment told investors it would take all available actions to improve its quality scores.


Rise and shine, everyone, another busy day is on the way. And it is getting off to a pleasant start here on the Pharmalot campus, where clear blue skies and comfy breezes are greeting us. As for the official mascots, they are happily snoozing in their respective corners. As for us, we are firing up the trusty kettle for another cup of stimulation. Our choice today is butter pecan. Of course, you are invited to join us. For the full experience, we are now hawking replicas — take a look. Meanwhile, here are a few items of interest. As always, do keep in touch. We appreciate feedback, criticism, and tips. …
Two months after the release of an open letter on potential safety issues tied to a rare disease drug sold by Neurocrine Biosciences, patient advocates and some experts are expressing growing alarm over the perceived risks of the therapy, STAT reports. The drug, approved to treat Prader-Willi syndrome, which can cause an insatiable feeling of hunger, has been linked to the deaths of seven people and the hospitalization of nearly 100 others — all since the treatment, called Vykat XR, was approved 18 months ago. Case reports on those deaths and hospitalizations that were submitted to regulators do not prove causality; many of the Vykat cases involved complex medical issues and multiple medications. But some experts say the evidence is sufficient to conclude Vykat is causing unacceptable harm.
The gifts and payments that doctors receive from drugmakers increased inappropriate prescribing and the number of prescriptions written, likely leading to rising health care costs, STAT writes, citing a Cochrane review of dozens of previous studies that have explored the influence the pharmaceutical industry has on medical practice. In addition, pharmaceutical advertising or education aimed at doctors may also increase inappropriate prescribing, probably increases the number of prescriptions written, and may increase the costs of prescriptions. But conflict-of-interest policies that restrict or manage interactions between companies and doctors probably improved prescribing practices.
STAT+ Exclusive Story
Already have an account? Log in
Already have an account? Log in
To read the rest of this story subscribe to STAT+.

A venture fund’s objective is to invest capital into early-stage companies to fuel growth, increasing the probability that they are acquired or reach public markets. That’s how an “exit” is achieved, with the invested capital returned at a risk-adjusted profit. Corporate venture capital (CVC) differs from orthodox venture capital because, alongside financial returns, a CVC’s goal is often to create strategic value for a core business.
Delivering this strategic value is much easier said than done, and therefore not well addressed by most CVC funds.
Outlined below are four distinct practices that optimize strategic and financial value.
Define strategic value alongside financial return
Strategic value comes in many forms. Pharma corporate venture should develop investments that might generate a valuable new target, drug, or vaccine candidate, improve the probability of pipeline success, reduce the cost of R&D, accelerate clinical trials — and more through the entire value chain. It is not necessary to acquire such businesses outright, but it is necessary to cultivate them into standardized, scaled solutions for scientists, regulators, clinicians, patients, and payors.
Assessing the value of an asset — financial and/or strategic — is as much art as science. Financial value can be estimated using discounted cash flow analysis, which relies on pro forma projections and assumptions about future market pricing and multiples, or through comparable-company analysis. Quantifying strategic value is much more difficult. One derivative indicator of strategic value is whether the core CVC business engages with the portfolio company, through piloting, partnering, licensing, and/or purchasing products or services. A CVC that can’t generate this type of engagement is just delivering capital without a strategic return.
Lead internal collaborations that power sourcing and diligence
Placing relevant strategic investments requires deep familiarity with the parent company’s objectives and priorities. This means dedicated internal workstreams with business leaders and subject matter experts who help refine and prioritize use cases and understand unmet needs. In-house CVC resources also help with pipeline building and technical, scientific, and clinical due diligence. Proper engagement is time-consuming and requires operational, process, and communication excellence — skills anathema to the normal concerns of most venture investors.
Many benefits accrue from generating that upfront buy-in. Deep collaboration raises the CVC’s probability of succeeding in highly scientific and technical markets. It also instills early business awareness and engagement, so portfolio companies develop faster pilots and larger partnerships, executable in a shorter timeframe.
Drive leverage through syndication
Most CVC investors are equipped to lead negotiations and price rounds, but there’s a strong case for prioritizing syndicate creation.
Syndication provides leverage through agile, coordinated activity on negotiating terms, dividing or delegating board activities, and considering future mergers and acquisitions. It also extends financial leverage, allowing a fund to cover more of the market and back a broader range of strategic interest areas. Joining syndicated deals priced by expert financial investors tends to produce a fair market price. A CVC can always walk away when pricing runs ahead of what its internal modeling supports.
Even with reduced board involvement, a fund can stay engaged through shareholder and information rights — quarterly financials, board materials, regular check-ins — whether it holds a board or observer seat or is simply an shareholder.
Occasionally, a CVC will need to play a more significant company-building role, In such cases it can place a convertible note or lead a round outright — but always with an eye toward delegating responsibility over time. The correct level of involvement is a case-by-case decision, considering the strategic relevance of the platform, the stage of the company, and the experience of its board and management team.
Deliver the payoff
None of this works as one single move, but as a pattern: sourcing shaped by internal collaboration, pricing and development sharpened by syndication, and continued engagement all the way to exit. Funds that operate this way tend to see their strategic and financial returns reinforce each other over time rather than trade off against one another.
The key lies in recruiting and training leaders who roll up their sleeves and work seamlessly with internal partners. When portfolio investments help a business develop better therapies or reach patients faster, they deliver strategic value — and ultimately value to patients and providers.
Photo: Hong Li, Getty Images

David M. Rubin, Ph.D., is a Managing Director in Merck GHIF, where he leads the drug discovery and precision medicine practice. Dr. Rubin ran and helped build life sciences companies in the USA, UK, Denmark, Hungary, and India. He was awarded National Institutes of Health and American Cancer Society Fellowships to support his research at Harvard Medical School on ubiquitin-dependent protein degradation. He received a B.A. in biology from SUNY Binghamton and a Ph.D. from Temple University. Junk Birds, his collection of previously published short stories, was published in 2025.
This post appears through the MedCity Influencers program. Anyone can publish their perspective on business and innovation in healthcare on MedCity News through MedCity Influencers. Click here to find out how.