The company says it will use the money to develop AI agents and deepen its relationships with its 30 health technology partners.

The company says it will use the money to develop AI agents and deepen its relationships with its 30 health technology partners.
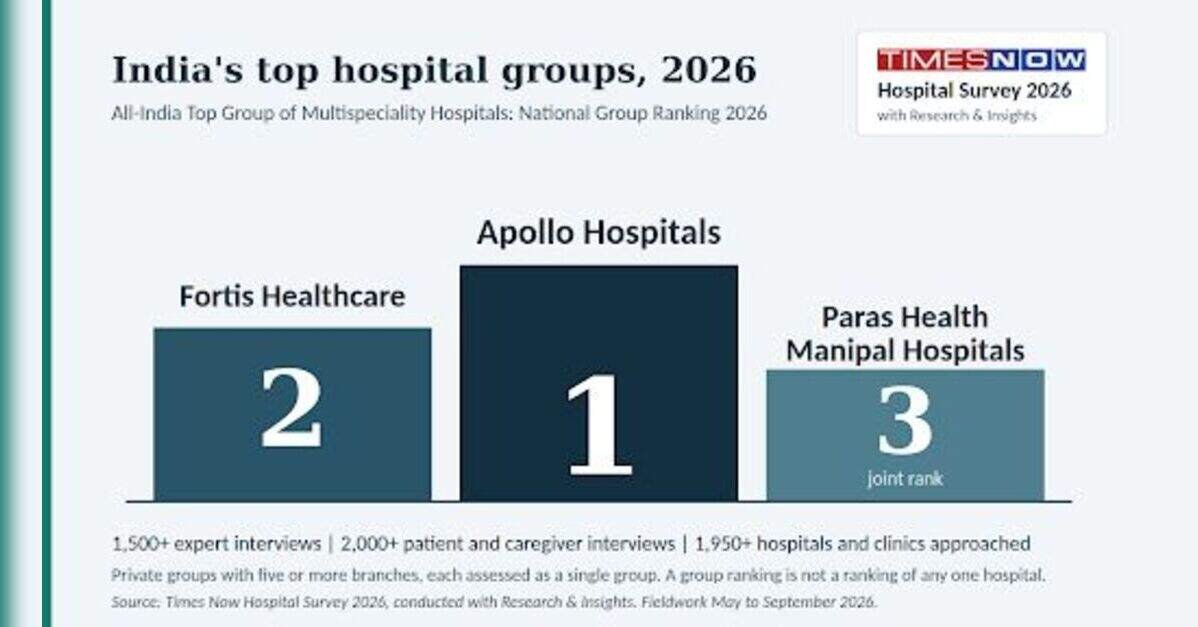
New Delhi, October 2026: Apollo Hospitals has secured the first position and Fortis Healthcare the second in the All-India Top Group of Multispeciality Hospitals – National Group Ranking 2026, conducted as part of the Times Now Hospital Survey 2026. Manipal Hospitals and Paras Health have jointly secured third place, bringing together four healthcare groups that represent different approaches to building and expanding multispeciality care in India.
Conducted by Times Now in association with research partner Research & Insights, the survey assessed private hospital groups as integrated healthcare networks rather than evaluating individual hospitals in isolation. The first results draw attention to a question facing India’s healthcare sector: how effectively can hospital groups maintain clinical capabilities, infrastructure and patient-care standards across multiple locations?
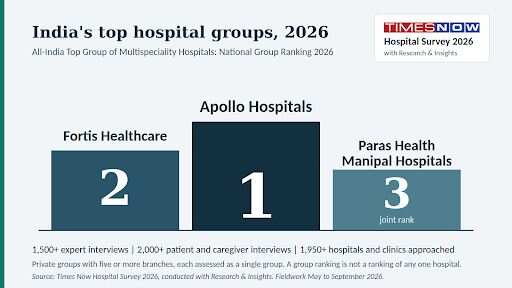
Source: Times Now Hospital Survey 2026, National Group Ranking.
The survey was conducted between May and September 2026. Its methodology combined desk research, more than 1,500 interviews with doctors and medical specialists, more than 2,000 interviews with patients and caregivers, and fact sheets sent to more than 1,950 hospitals and clinics. The assessment combined expert and patient perceptions with factual information on clinical quality, infrastructure, human resources, accreditation, patient safety, and academic and research capability.
Only private hospital groups with at least five operational branches were eligible. Government, partly government-funded, charitable and not-for-profit hospitals were excluded. The results reflect each eligible group as a single entity and should not be read as rankings of individual campuses. The survey also allows the same rank where the statistical gap between two entities is very small, as in the joint third place.
Figures in this section are as published by the groups on their own websites in October 2026.
Apollo Hospitals, which secured the first position, says it opened India’s first corporate hospital in 1983 and has since built a broad healthcare ecosystem spanning hospitals, pharmacies, diagnostics and primary-care clinics. The group reports more than 10,000 beds and a pharmacy network of over 4,000 outlets. Its scale reflects how organised private healthcare has moved from individual institutions to interconnected networks.
Fortis Healthcare, ranked second, reports 36 healthcare facilities across 12 states, with more than 6,000 operational beds, spanning hospitals, diagnostics and day-care specialty facilities. Its stated mission centres on clinical excellence and patient care.
Manipal Hospitals, which shares third place, traces its roots to the founding of Kasturba Medical College in 1953, with its first hospital opening in Bengaluru in 1991. The group reports 49 hospitals in more than 24 cities and over 12,600 beds, and says its network is expanding across metro and tier-II cities.
Paras Health’s joint third place brings a different dimension to the ranking: the development of advanced multispeciality care in markets where specialised treatment has often been harder to find close to home.
While much of India’s organised private healthcare infrastructure has historically been concentrated in the major metros, Paras Health has built a network across northern and eastern India, largely in cities beyond the largest metropolitan centres. Its eight hospitals are in Gurugram and Panchkula in Haryana, Patna and Darbhanga in Bihar, Ranchi in Jharkhand, Udaipur in Rajasthan, Kanpur in Uttar Pradesh and Srinagar in Jammu & Kashmir, a presence in five states and one Union Territory.
According to its website, Paras Health describes itself as having 20 years in healthcare, has treated more than 2.1 million patients across multiple states, and has a team of more than 2,100 doctors and nurses. Its clinical services include cardiac sciences, oncology, neurosciences, gastro sciences, orthopaedics, renal sciences, and liver transplant and GI surgery, among other specialties. The group’s Srinagar hospital marked three years in May 2026.
Building a multispeciality hospital outside an established metropolitan hub takes more than physical infrastructure. Hospitals must attract and retain experienced clinicians, establish multidisciplinary teams, invest in specialised equipment, maintain quality and patient-safety systems, and develop the operational capability to support complex treatments.
These requirements can be harder to meet in Tier-II and Tier-III markets, where specialised clinical talent, supporting medical infrastructure and referral networks may differ from those in larger cities, and where providers must balance affordability against the cost of advanced services. For patients, having such services locally can reduce the need to travel to metropolitan centres for consultations, diagnostics and treatment.
Paras Health’s presence in Patna, Darbhanga, Ranchi, Kanpur, Udaipur and Srinagar illustrates an emphasis on building this capacity outside the largest markets. Manipal’s presence across metro and tier-II markets shows how established national networks are also broadening their reach. The two approaches differ in scale and geography, but both point to the growing importance of extending organised healthcare beyond traditional urban centres.
The challenge is not simply to open hospitals in more cities, but to sustain clinical capability, patient experience and quality systems across an entire network. The Times Now survey assesses groups against that institutional perspective. However, the published ranking does not provide criterion-wise scores showing that any single strategy or factor determined a group’s position. Paras Health’s joint third place should therefore be read as a national group-level outcome, with its expansion model an illustration of the wider shift towards advanced care in non-metropolitan India.
The first release of the Times Now Hospital Survey 2026 places Apollo Hospitals, Fortis Healthcare, Manipal Hospitals and Paras Health within the national conversation on organised multispeciality healthcare. Their positions bring different network models into focus, from the scale of established national chains to the development of advanced care in markets beyond the largest cities. As hospital networks continue to expand, the ability to sustain clinical capability across locations will remain an important consideration for patients, healthcare professionals and the wider industry.
The survey’s campus-level, specialty, zonal and city-level results, being released in stages, are expected to add further perspective on individual hospitals and healthcare markets.
About the survey: The Times Now Hospital Survey 2026 was conducted by Times Now in association with Research & Insights. It assesses eligible private hospitals and hospital groups through desk research, medical-expert interviews, patient and caregiver interviews, and factual hospital data. Results are being released in stages across national group, hospital, specialty, zonal and city categories.
A note on the figures: Network figures for Apollo Hospitals, Fortis Healthcare, Manipal Hospitals and Paras Health are as published on each group’s website in October 2026 and may change. Survey details are from the Times Now Hospital Survey 2026 methodology.
Disclaimer: The above content is non-editorial, and TIL hereby disclaims any and all warranties, expressed or implied, relating to it, and does not guarantee, vouch for or necessarily endorse any of the content.


As a rheumatologist, I treat rheumatoid arthritis (RA) and other complex autoimmune diseases. If you have or happen to develop one of these diseases, I am thankful that science has delivered amazingly effective targeted therapeutics and biologics in recent decades. While highly effective, these treatments come with a high economic cost, so I have grown accustomed to daily battles with commercial insurance plans to get working-age patients the treatments they need. While horror stories abound regarding commercial insurers, Medicare has traditionally been a more predictable partner for my older patients. Medicare reimbursement is low — an issue worthy of a separate commentary piece — but comes on time, typically without the hassle and administrative delays of prior authorizations, assuming we use our therapeutics within FDA-approved dosing and indications.
On top of these existing challenges here in the Midwest, providers recently won a battle we did not expect to have to fight with a Medicare administrative contractor (MAC). The story deserves scrutiny from legislators and regulators nationwide.
Medicare beneficiaries rightly assume, as have I, that policy spells out the services they are entitled to receive. Lawmakers in Congress establish patients’ benefits in law, while the Centers for Medicare & Medicaid Services (CMS) develops the national rules and policies to implement them. MACs fit into this process by administering those rules regionally (with some discretion), but they are not supposed to privately create new substantive conditions of payment.
Recently, the MAC overseeing Kentucky and Ohio began auditing and denying claims for intravenous Orencia, a biologic drug used to treat RA, citing a “lack of medical necessity.” The policy affected more than a hundred patients who had mostly been on Orencia for a decade or more. These patients were forced to stop or delay treatment or switch therapies, which resulted in serious RA flares. MAC administrators had decided that most patients on intravenous Orencia, covered under Medicare Part B, should instead receive subcutaneous Orencia, covered under Medicare Part D and often at substantially higher out-of-pocket cost.
The decision was made without a formal notice-and-comment process. In fact, this requirement does not even appear in the Medicare guidance cited for this decision. Worst of all, it effectively forced dozens of patients off a life-changing therapy.
Thanks to outreach from clinicians, national advocacy organizations, angry patients, and congressional representatives, this policy was walked back. Or at least, we think so. There was no announcement of a reversal. Instead, the MAC covering Kentucky and Ohio quietly revised a fact sheet on its website, removing language that preferred subcutaneous over intravenous dosing.
This whiplash has been devastating to my own small clinic, however, as the MAC continues to withhold the equivalent of roughly three payrolls’ worth of payments for treatments we rendered in good faith during this period. They have also not answered repeated inquiries about whether denials issued under the now-removed standard will be reversed.
This situation exposed several problems that need to be addressed before this happens to other MACs, Medicare beneficiaries and clinicians:
1. The current system allowed one medical director’s opinion to acquire the force of Medicare policy without an effective check. This violates the Supreme Court’s decision in Azar v. Allina, which limits the government’s ability to create substantive Medicare payment standards through informal guidance. Yet it still took months of work, worry, and countless hours distracted from providing clinical care to get the issue elevated to a level where the policy was reconsidered.
2. There is inadequate accountability and little transparency within MAC operations. After an initial call with the MAC medical director to raise this issue, we went for weeks with response and no clue as to where our appeal stood. Providers didn’t know how to “correctly” care for our affected patients. When the disputed language did quietly disappear from the fact sheet, there was no public explanation, formal announcement, or directive regarding claims already denied.
3. There is no clearly identified chain of command to move a critical issue of patient harm from a regional MAC to CMS. As an experienced advocate, I leveraged my relationship with my congressional representative and the American College of Rheumatology to elevate this issue to CMS, but what if I hadn’t had those relationships? Our system should not require physicians to become experts in Medicare law and policy just to ensure the Medicare system follows its own rules.
Medicare beneficiaries deserve better. While in this case we’ve been able to protect access to intravenous Orencia, this experience exposed flaws that extend far beyond one drug or one MAC contractor. We should all be concerned that MACs are increasingly making unilateral decisions that negatively impact patient access. Medicare policy should be transparent and include appropriate notice and stakeholder input. And when a contractor gets it wrong, there should be a clear and rapid way to stop the harm to patients, their relationship with their doctor and the doctor’s practice. A patient’s access to Medicare-covered care should never depend on whether their physician can find someone in Washington willing to intervene. Something must change.
Author bio:
Dr. Chris Phillips is an American College of Rheumatology leading rheumatologist and owner of Paducah Rheumatology.
Photo: Stas_V, Getty Images


The lawsuit isn’t a surprise, after Alignment told investors it would take all available actions to improve its quality scores.

A venture fund’s objective is to invest capital into early-stage companies to fuel growth, increasing the probability that they are acquired or reach public markets. That’s how an “exit” is achieved, with the invested capital returned at a risk-adjusted profit. Corporate venture capital (CVC) differs from orthodox venture capital because, alongside financial returns, a CVC’s goal is often to create strategic value for a core business.
Delivering this strategic value is much easier said than done, and therefore not well addressed by most CVC funds.
Outlined below are four distinct practices that optimize strategic and financial value.
Define strategic value alongside financial return
Strategic value comes in many forms. Pharma corporate venture should develop investments that might generate a valuable new target, drug, or vaccine candidate, improve the probability of pipeline success, reduce the cost of R&D, accelerate clinical trials — and more through the entire value chain. It is not necessary to acquire such businesses outright, but it is necessary to cultivate them into standardized, scaled solutions for scientists, regulators, clinicians, patients, and payors.
Assessing the value of an asset — financial and/or strategic — is as much art as science. Financial value can be estimated using discounted cash flow analysis, which relies on pro forma projections and assumptions about future market pricing and multiples, or through comparable-company analysis. Quantifying strategic value is much more difficult. One derivative indicator of strategic value is whether the core CVC business engages with the portfolio company, through piloting, partnering, licensing, and/or purchasing products or services. A CVC that can’t generate this type of engagement is just delivering capital without a strategic return.
Lead internal collaborations that power sourcing and diligence
Placing relevant strategic investments requires deep familiarity with the parent company’s objectives and priorities. This means dedicated internal workstreams with business leaders and subject matter experts who help refine and prioritize use cases and understand unmet needs. In-house CVC resources also help with pipeline building and technical, scientific, and clinical due diligence. Proper engagement is time-consuming and requires operational, process, and communication excellence — skills anathema to the normal concerns of most venture investors.
Many benefits accrue from generating that upfront buy-in. Deep collaboration raises the CVC’s probability of succeeding in highly scientific and technical markets. It also instills early business awareness and engagement, so portfolio companies develop faster pilots and larger partnerships, executable in a shorter timeframe.
Drive leverage through syndication
Most CVC investors are equipped to lead negotiations and price rounds, but there’s a strong case for prioritizing syndicate creation.
Syndication provides leverage through agile, coordinated activity on negotiating terms, dividing or delegating board activities, and considering future mergers and acquisitions. It also extends financial leverage, allowing a fund to cover more of the market and back a broader range of strategic interest areas. Joining syndicated deals priced by expert financial investors tends to produce a fair market price. A CVC can always walk away when pricing runs ahead of what its internal modeling supports.
Even with reduced board involvement, a fund can stay engaged through shareholder and information rights — quarterly financials, board materials, regular check-ins — whether it holds a board or observer seat or is simply an shareholder.
Occasionally, a CVC will need to play a more significant company-building role, In such cases it can place a convertible note or lead a round outright — but always with an eye toward delegating responsibility over time. The correct level of involvement is a case-by-case decision, considering the strategic relevance of the platform, the stage of the company, and the experience of its board and management team.
Deliver the payoff
None of this works as one single move, but as a pattern: sourcing shaped by internal collaboration, pricing and development sharpened by syndication, and continued engagement all the way to exit. Funds that operate this way tend to see their strategic and financial returns reinforce each other over time rather than trade off against one another.
The key lies in recruiting and training leaders who roll up their sleeves and work seamlessly with internal partners. When portfolio investments help a business develop better therapies or reach patients faster, they deliver strategic value — and ultimately value to patients and providers.
Photo: Hong Li, Getty Images

David M. Rubin, Ph.D., is a Managing Director in Merck GHIF, where he leads the drug discovery and precision medicine practice. Dr. Rubin ran and helped build life sciences companies in the USA, UK, Denmark, Hungary, and India. He was awarded National Institutes of Health and American Cancer Society Fellowships to support his research at Harvard Medical School on ubiquitin-dependent protein degradation. He received a B.A. in biology from SUNY Binghamton and a Ph.D. from Temple University. Junk Birds, his collection of previously published short stories, was published in 2025.
This post appears through the MedCity Influencers program. Anyone can publish their perspective on business and innovation in healthcare on MedCity News through MedCity Influencers. Click here to find out how.


Bengaluru: Alcon announced the launch of Clareon PanOptix Pro intraocular lens (IOL) for cataract patients in India.
The company said the new lens uses its proprietary ENLIGHTEN NXT optical technology which delivers the lowest light scatter and highest reported light utilization of any trifocal IOL.
According to Alcon, PanOptix Pro provides 94 per cent light utilisation, compared to a theoretical maximum utilization of 96 per cent for diffractive optics.
“PanOptix Pro offers powers ranging from +6.0 through +30.0 diopters (in 0.5 diopter increments), +31.0 through +34.0 diopters (in 1.0 diopter increments) with a +2.17 diopter intermediate and a +3.25 diopter near add power,” Alcon added.


Pune: AI-led medical tourism platform, CureMeAbroad, has expanded into Australia with a network of experience centres across multiple locations.
The company said it has signed an MoU to anchor the rollout with 40 experience centres planned to open across Australia, the US and the UK.
The company said its first centre in Australia will open in Brisbane giving patients an in-person place to begin their treatment journey.
They will connect to CureMeAbroad’s digital platform, which gives patients access to more than 400 partner hospitals across Turkey, Thailand, India, Mexico, Georgia and other destinations.


New Delhi: People who developed an early onset of Alzheimer’s disease — before turning 65 — displayed symptoms and conditions different to those in late-onset Alzheimer’s, accumulating a wide range of health problems, particularly during the five years preceding diagnosis, a study has found.
Researchers from the University of Oulu and the University of Eastern Finland said the group is more likely to experience depression, dizziness, headaches, traumatic brain injuries, epilepsy, cerebrovascular disorders, thyroid diseases and problems related to heavy alcohol use.
Tinnitus (ringing in ears) and hearing loss were already more common six to ten years before diagnosis, findings published in the journal Alzheimer’s and Dementia: The Journal of the Alzheimer’s Association showed.
However, cardiovascular risk factors traditionally associated with Alzheimer’s disease were found to be no more common among those diagnosed at working age, compared to age- and sex-matched healthy people.
Cardiovascular risk factors, alongside advanced age, are among the best-known risk factors for the neurodegenerative disease, the researchers said.
However, compared to late-onset Alzheimer’s disease, high blood pressure and hyperlipidemia were not more common among people with early-onset Alzheimer’s disease than among the control group, they said.
“Our findings support the view that early-onset Alzheimer’s disease is not simply a younger-age version of late-onset Alzheimer’s disease. Rather than the familiar cardiovascular risk factors, we observed a range of other health problems becoming more common as diagnosis approached,” lead researcher Johanna Kruger, adjunct professor from the University of Oulu, said.
The researchers also found no significant differences in morbidity 11 to 15 years before diagnosis, suggesting that identifiable changes begin to emerge mainly closer to disease onset.
The findings indicate that early-onset Alzheimer’s disease may involve mechanisms that differ, at least in part, from those underlying late-onset Alzheimer’s disease, they said.
Healthcare utilisation was found to have increased markedly during the five years leading up to diagnosis, alongside a growing burden of health conditions. The steepest increase in healthcare visits was seen to occur during the final year before Alzheimer’s disease was diagnosed.
The study’s findings are based on patient data from memory clinics at Oulu University Hospital and Kuopio University Hospital, combined with nationwide health register data.
The study included 407 people with early-onset Alzheimer’s disease, whose health records were compared with those of more than 4,000 age- and sex-matched people without the neurodegenerative disease. Diseases and health conditions were examined that occurred during the 15 years preceding an Alzheimer’s disease diagnosis.
“EOAD (early onset Alzheimer’s disease) patients had higher prevalence of vertigo, depression, headache, delirium, brain injuries, thyroid disorders, alcohol-related disorders, epilepsy, strokes, and otorhinolaryngologic diseases 1-5 years before diagnosis,” the authors wrote.


UnitedHealth raised its 2026 earnings guidance and outperformed analyst expectations for the third time this year, suggesting its financial turnaround is sustainable.
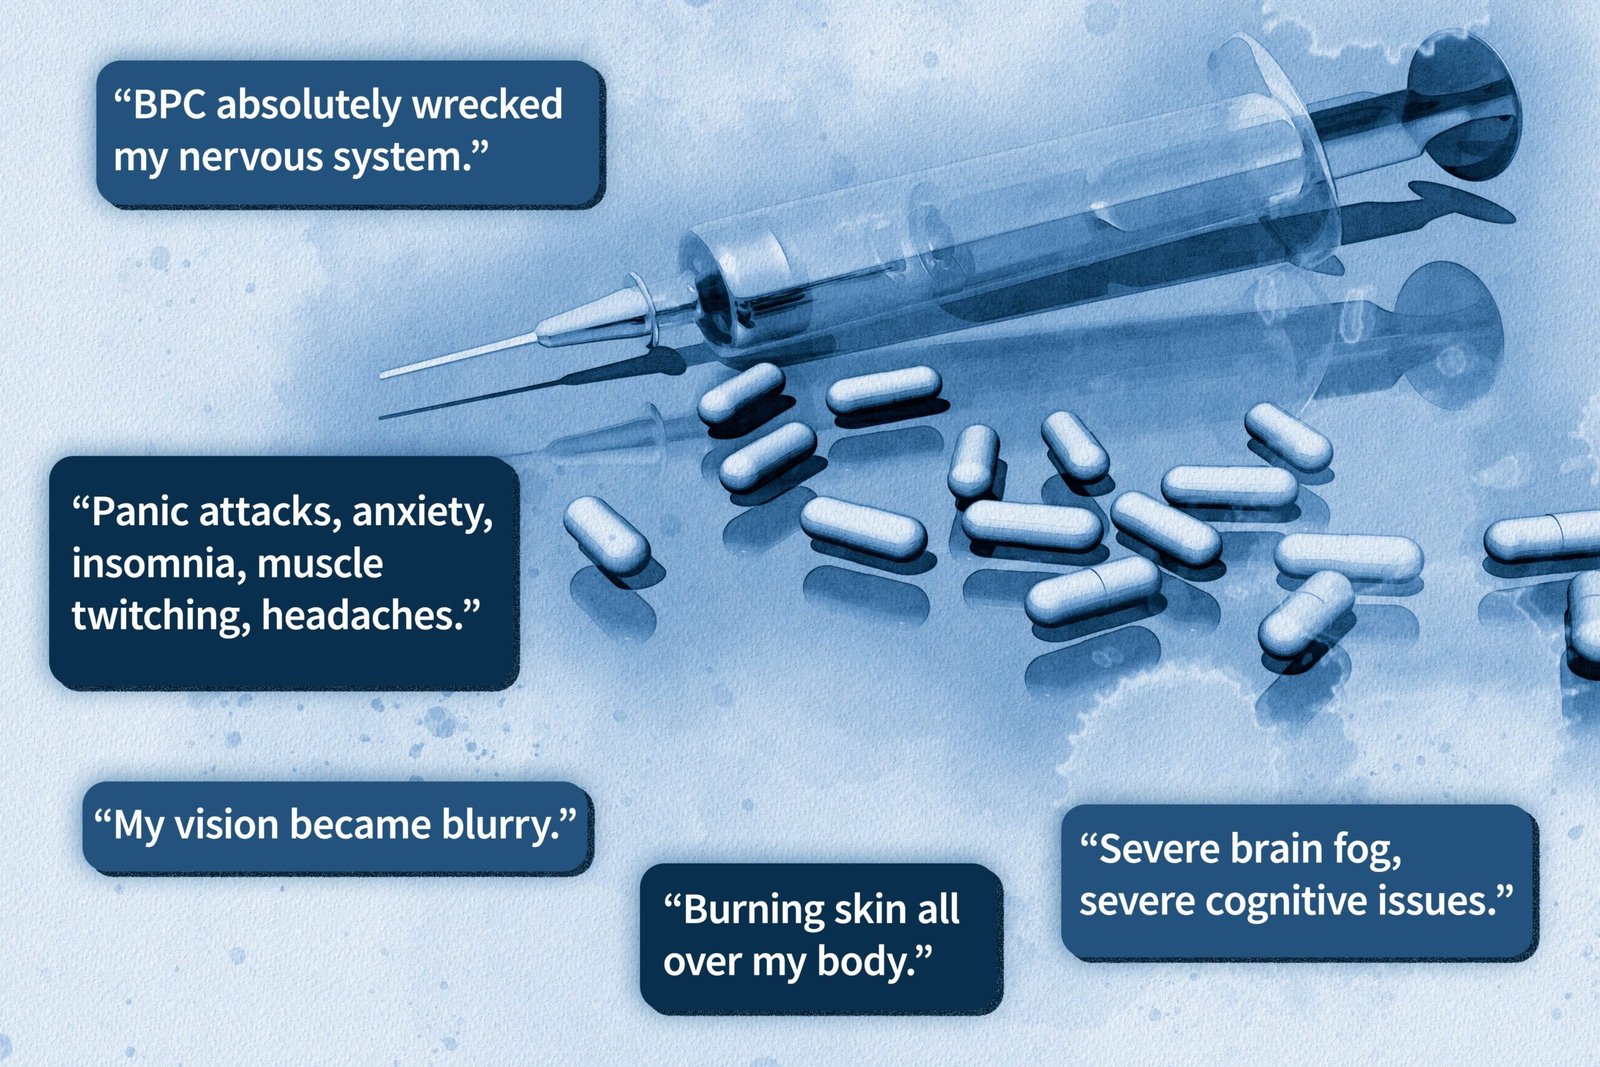
After the third day of squirting an experimental drug up his nose, Dylan Meetze felt horrible.
“It was like I was underwater, like it took the most to do anything,” he said.
Meetze stopped taking the drug but endured fatigue and anxiety for months afterward, and his eyes and muscles twitched, he said.
He had taken BPC-157, a peptide drug popularized by podcasts about wellness, longevity, and what’s called “body optimization.” “Peptide” is a general term for substances that are smaller than proteins but composed of the same building blocks. Dozens of peptide drugs, including insulin and GLP-1 weight loss medicines, have garnered approval by the Food and Drug Administration. But BPC-157 and many others have not because they haven’t undergone clinical trials.
This fact hasn’t stopped online influencers from promoting them as remedies for muscle injuries, gut issues, covid, and more. Use of BPC-157 is growing in the U.S., particularly among white males, according to a new analysis of millions of de-identified electronic health records. Since 2020, the analysis, which hasn’t yet been published in a peer-reviewed journal, found that more than 1,000 people told doctors they had used the drug.
Meetze said he decided to take BPC-157 after listening to Andrew Huberman, a Stanford neuroscientist with more than 16 million followers on YouTube, Instagram, and TikTok, who talks up peptides frequently on his podcasts. Studies in mice suggest that BPC-157 helps muscles heal and has “very high safety profiles,” Huberman has said, “at least, with respect to the lethal dosing.” His guest on one episode, Craig Koniver, a doctor who sells peptides through his wellness clinic, called BPC-157 “super safe” and recommended it for “anyone who’s working out on a regular basis.” Koniver did not respond to requests for comment.
Huberman didn’t respond to multiple queries from KFF Health News, but an automatic reply linked to a disclaimer on his Huberman Lab website that says the podcast doesn’t constitute medical advice: “Any reliance on information provided through the podcast is solely at the user’s own risk.”
Hoping BPC-157 might help him advance as a weightlifter, Meetze said he bought the drug last year from an online vendor, Researchem. A chemical supply company with that name sells experimental peptides through its website, warning that the substances are “solely for laboratory research” and are “not intended for human consumption.” (It lists an address in Hillsboro, Oregon, that corresponds to a shared office space. A receptionist at the space said Researchem wasn’t registered there, and multiple queries from KFF Health News to the email address listed on the website went unanswered.)
Companies are required to warn that experimental peptides, which haven’t been approved by the FDA, are for research use only. But many companies may soon be permitted to drop the warning because of a push by health secretary Robert F. Kennedy Jr. to lower barriers to their use. He and other leaders of the Make America Healthy Again movement have promoted peptides as a way to improve the country’s health.
On the social media platform X, before he took the helm at the Department of Health and Human Services, Kennedy vowed to end the “aggressive suppression” of “peptides, stem cells, raw milk” and “anything else that advances human health and can’t be patented by Pharma.” (In fact, peptides are heavily patented.)
He has repeated the pledge since taking office. On Joe Rogan’s podcast early this year, Kennedy said he was a “big fan” of peptides and wanted to make many of them “more accessible.” On a podcast with the co-chair of the MAHA Action committee, Gary Brecka, Kennedy said the FDA’s role should be to assess science, “but not tell people and not tell physicians what they can and cannot prescribe.”
“If you want to take an experimental drug,” he added, “you ought to be able to do that.”
This summer, Kennedy’s health department appointed doctors with financial stakes in the peptide industry to a panel that advises the FDA. At an FDA meeting in July, the new appointees voted to ease restrictions on six experimental peptides, including the trendy compounds BPC-157, TB-500, and MOTS-c. Specifically, they advised adding these peptides to a list, called 503A, that would allow specialized pharmacies to make the drugs for human use, even though the FDA hasn’t approved them.
In an email, HHS spokesperson Emily Hilliard wrote that every committee member satisfies the FDA’s ethics requirements. “FDA — not podcasts or politics — determines which substances qualify for inclusion on the 503A Bulks List,” she wrote. The FDA has yet to issue a final decision.
The vote went against FDA scientists who presented research on the six peptides, concluding there wasn’t enough evidence to show they improved any condition. Furthermore, the scientists highlighted a potential for liver damage, allergic reactions, or other serious consequences.
“People are saying this is about medical freedom — putting decisions back in the hands of patients,” said Reshma Ramachandran, a regulatory science researcher at Yale School of Medicine. “But what we see in practice is that incentives aren’t actually centered around patients. They’re centered around selling products.”
Scientists also warned that drugmakers would be reluctant to invest millions of dollars into clinical trials on peptides if they could be sold without FDA approval.
“The chances of clinical trials getting done now are diminished,” said Eric Topol, executive vice president of Scripps Research, a biomedical science institute in San Diego. “We will have more people who are prey to predators that will sell, sell, sell.”
A lack of data leaves consumers in the dark.
Meetze sought help on Reddit, where people post about pain, headaches, vision problems, and a lack of motivation after taking experimental peptides. Peptide enthusiasts often comment on these posts with skepticism, attributing a person’s problems to contaminated products, preexisting conditions, or misuse of the drugs. The online vitriol in the Reddit conversations can be intense, so Meetze welcomed an invitation to join a private group on the social platform Discord in which people with BPC-157 side effects tried to figure out what happened to them and how to fix it.
“There are millions of success stories with these peptides,” Meetze said, “but no one wants to believe that this wrecks some of our lives.”

Wolverines and Migraines
One member of the private side-effects group, a 46-year-old software engineer named Dominik E., said he got an excruciating migraine within days of taking BPC-157 with TB-4, another unapproved peptide — a combination called the “Wolverine Stack” because of its purported ability to heal wounds rapidly, like its namesake Marvel superhero.
“My left eye started throbbing really badly, and the left side of my face became numb,” he told KFF Health News, which agreed to only partially identify him and others interviewed for this article who were concerned about divulging sensitive health information.
After two months of migraines, Dominik said, the pain eased, but his face felt inflamed. “It is a total nightmare,” he said.
“I’m afraid how people will judge me,” said Lois S., a woman who works at a Michigan elementary school. She hoped BPC-157 and another unapproved peptide, retatrutide, would help with weight loss, but she stopped taking the treatment when she felt pain.
“I sought out this substance from a lab that clearly labeled it not for human use, purchased a syringe, and injected this in my kitchen,” she said. “That belies all logic about what a normal person would do.”
Peptide proponents argue that shoddy manufacturing — not the peptides — causes harm. Therefore, they say, the FDA must protect the public by allowing doctors to prescribe peptides made for human use by pharmacies that specialize in compounding medicines. Typically, compounding pharmacies manufacture alternatives to FDA-approved drugs so a patient can, say, get a liquid version of a drug that the original manufacturer makes only as pills.
Adding unapproved peptides to the FDA’s list of compoundable drugs would mark a departure from the list’s purpose, said Peter Lurie, a former FDA official who now directs the advocacy group Center for Science in the Public Interest. He noted that federal and state oversight for compounding pharmacies is often lax, and they’ve been cited for contamination.
Furthermore, he added, the move would mislead consumers into thinking they’re buying drugs backed by clinical trials. People promoting peptides often point to promising laboratory research as evidence. Rats with spinal injuries regained tail mobility after BPC-157 injections, for example, and old mice given the experimental peptide MOTS-c could run longer. On average, however, fewer than 10% of substances that show promise in animal studies prove effective in clinical trials.
“A lot of this pseudoscience stuff sounds deeply impressive — inflammation this and telomere that — but at the end of the day, none of it really matters,” Lurie said. “You’ve got to show clinical benefit in humans: Does it work?”
Peptide promoters lean on anecdotes, often without verifiable numbers. In a podcast recorded at the White House, the MAHA influencer Brecka said: “Twenty million people have been prescribed these things without adverse events.” His guest on the episode, Brigham Buhler — who is the co-author of The Peptide Revolution and owner of a compounding pharmacy that sells peptides and a clinic, Ways2Well, that prescribes them — told Brecka that none of its 75,000-plus patients had reported adverse events from peptides.
Buhler cited even higher numbers in the movie MAHA Uncensored, a documentary featuring Kennedy and other leaders of the MAHA movement and that bears the MAHA trademark. In the segment on peptides, Buhler said: “Having treated literally hundreds of thousands of people through our compounding pharmacy, we’ve never had a major adverse event.”
Topol asks why those boasting success haven’t conducted clinical studies. “If influencers and companies really believe these peptides are helping people,” Topol said, “then they should put their profits back into rigorous research.”
Chris Woodward, a spokesperson for Brecka and his company, the Ultimate Human, said in an email that the health and wellness issues discussed on Brecka’s podcast do not constitute medical advice. “Mr. Brecka consistently advises his audience to consult a licensed physician,” Woodward wrote. Buhler did not respond to requests for comment.
Not all anecdotes are rosy. At an antiaging conference last summer in Las Vegas, two women were rushed to the hospital and intubated after being injected with experimental peptides and vitamins, according to citations that Nevada’s state pharmacy board issued against the doctor running the booth and his colleagues for prescribing and administering drugs without a state medical license.
An FDA database for adverse events contains concerning reports. Although the database can’t prove that a drug, vaccine, or medical device caused harm — the reports are brief, unverified, and voluntary — it signals issues worth exploring. A 36-year-old woman was hospitalized in December after taking the experimental peptide BPC-157 for weight control and a skin disorder, for example, and a 48-year-old man was hospitalized with a “life-threatening” condition after taking the peptide.
FDA scientists presented some of these reports at the July meeting and flagged worrisome outcomes in animal experiments, such as a 2020 study revealing signs of liver toxicity in rats and dogs injected with BPC-157.
Brian Lee, a liver disease specialist at the University of Southern California, was among the panel’s minority who voted against easing restrictions. Without clinical studies, he said, afflictions that take time to develop, like liver damage and cancer, might not be spotted for years: “I think this endorsement can be potentially harmful, and I cannot in good conscience vote ‘yes.’”
The panel’s newcomers disagreed. “I do not believe the FDA made a good case on issues with safety with BPC,” said Kris Wusterhausen, founder of an antiaging company in Texas, the Resurge Clinic, which sells a BPC-157 product for $149.
“Once you’ve seen the effects of BPC,” he said, “you can’t unsee it.”
Awaiting Trial
Deepak Srivastava, president of the Gladstone Institutes in San Francisco, designed a clinical trial two decades ago to see if a peptide he studies, TB-4, could repair tissue after a heart attack. Before enrollment, people volunteering for the study would be screened for early signs of cancer because TB-4 triggers vessel growth and cell migration, which might exacerbate malignant growths. He worries about the FDA panel’s vote to ease restrictions on a derivative of TB-4, before such trials have been completed, saying, “You need to have a healthy respect for the fact that drugs can be harmful.”
Pinchas Cohen, a peptide researcher at the University of Southern California, was less cautious, saying the FDA buzz might drive investors to fund trials. He’s seeking support to bring a peptide his lab identified, MOTS-c, to market. It’s “un-ideal” for people to take unproven drugs, Cohen said, but that’s what’s happening: “The world is changing and people like me need to accept that this is the new reality and find ways to make it as safe as possible.”
In the meantime, people like Meetze resort to podcasts and online forums for advice. His symptoms faded after a year, but he still had spells of feeling “zero emotions.”
Peptide users describe this condition as anhedonia. It’s come up on Huberman’s podcasts.
Huberman occasionally mentions other potential peptide risks, like cancer, sprinkling them into advice on how to take them. Take a 2024 episode with 1.2 million views: “I do not think that BPC-157 is not without its quote-unquote ‘side effects,’” Huberman says. “If you’re going to go down this path of taking BPC-157, I would encourage you to take the minimal effective dose, to not simply do it every day, and certainly to not do it continuously, and of course to monitor your other health metrics for anything that could potentially resemble cancer or tumor growth, because obviously stimulating angiogenesis for wound repair sounds like a great thing, recovering and being able to do your workouts or play your sport, or move about more comfortably, of course, a wonderfully attractive thing to do.”
“Isn’t that what we all want? But obviously not with the trade-off of growing a tumor,” he said, before interrupting the discussion to advertise a supplement company sponsoring the show.