Category: Hospitals

  • Medical Debt Is Crushing Hospital Patients in Los Angeles. Health Officials May Have a Fix.

    Medical Debt Is Crushing Hospital Patients in Los Angeles. Health Officials May Have a Fix.

    LOS ANGELES — Every Tuesday, Naman Shah sees tuberculosis patients at a small public clinic in Los Angeles’ San Fernando Valley. Shah, a physician and epidemiologist at the Los Angeles County Department of Public Health, pores over images of battered lungs, listens to labored breathing, and checks medications.

    It’s part of an initiative dating to the early 20th century to control infections so tuberculosis doesn’t spread. “We like doing things upstream,” Shah said, “meaning before they happen, not after the damage is done.”

    Today, Shah and his colleagues are applying the same principle to medical debt. A key part of that effort is a new system to allow every hospital in Los Angeles County to easily screen patients for financial aid. The goal: to stop low-income families from getting a bill that buries them in debt.

    Shah estimates this system could prevent several hundred million dollars of medical debt every year.

    Vicious Cycle

    Nationwide, an estimated 100 million adults have some form of healthcare debt. In Los Angeles County, the nation’s most populous, public health officials calculate that about 800,000 residents have medical bills they can’t pay.

    “The impacts of medical debt were staggering,” said Shah, who used to staff a rural health clinic in India and, since 2023, has led a county initiative in Los Angeles to tackle the debt problem.

    “People end up with credit card debt and then a vicious cycle of high interest rates and poverty,” he said. “People forgo their prescriptions. People forgo appointments. And then you get into worse health.”

    Hospitals typically offer financial aid to patients with low incomes. But information about assistance is often hard for patients to get. Applying can be cumbersome. And many eligible patients never seek aid, research shows.

    “Most people walk into the hospital and walk out without any knowledge of financial assistance,” said Jared Walker, founder of Dollar For, a nonprofit that helps patients nationwide apply for aid, often called charity care.

    That’s fueling debt. It’s also driving costly collection efforts that even hospital officials acknowledge pointlessly target low-income patients who are unlikely to be able to pay.

    “They’re turning their wheels trying to collect on debt that isn’t collectable,” said Adena Tessler, regional vice president for the Hospital Association of Southern California.
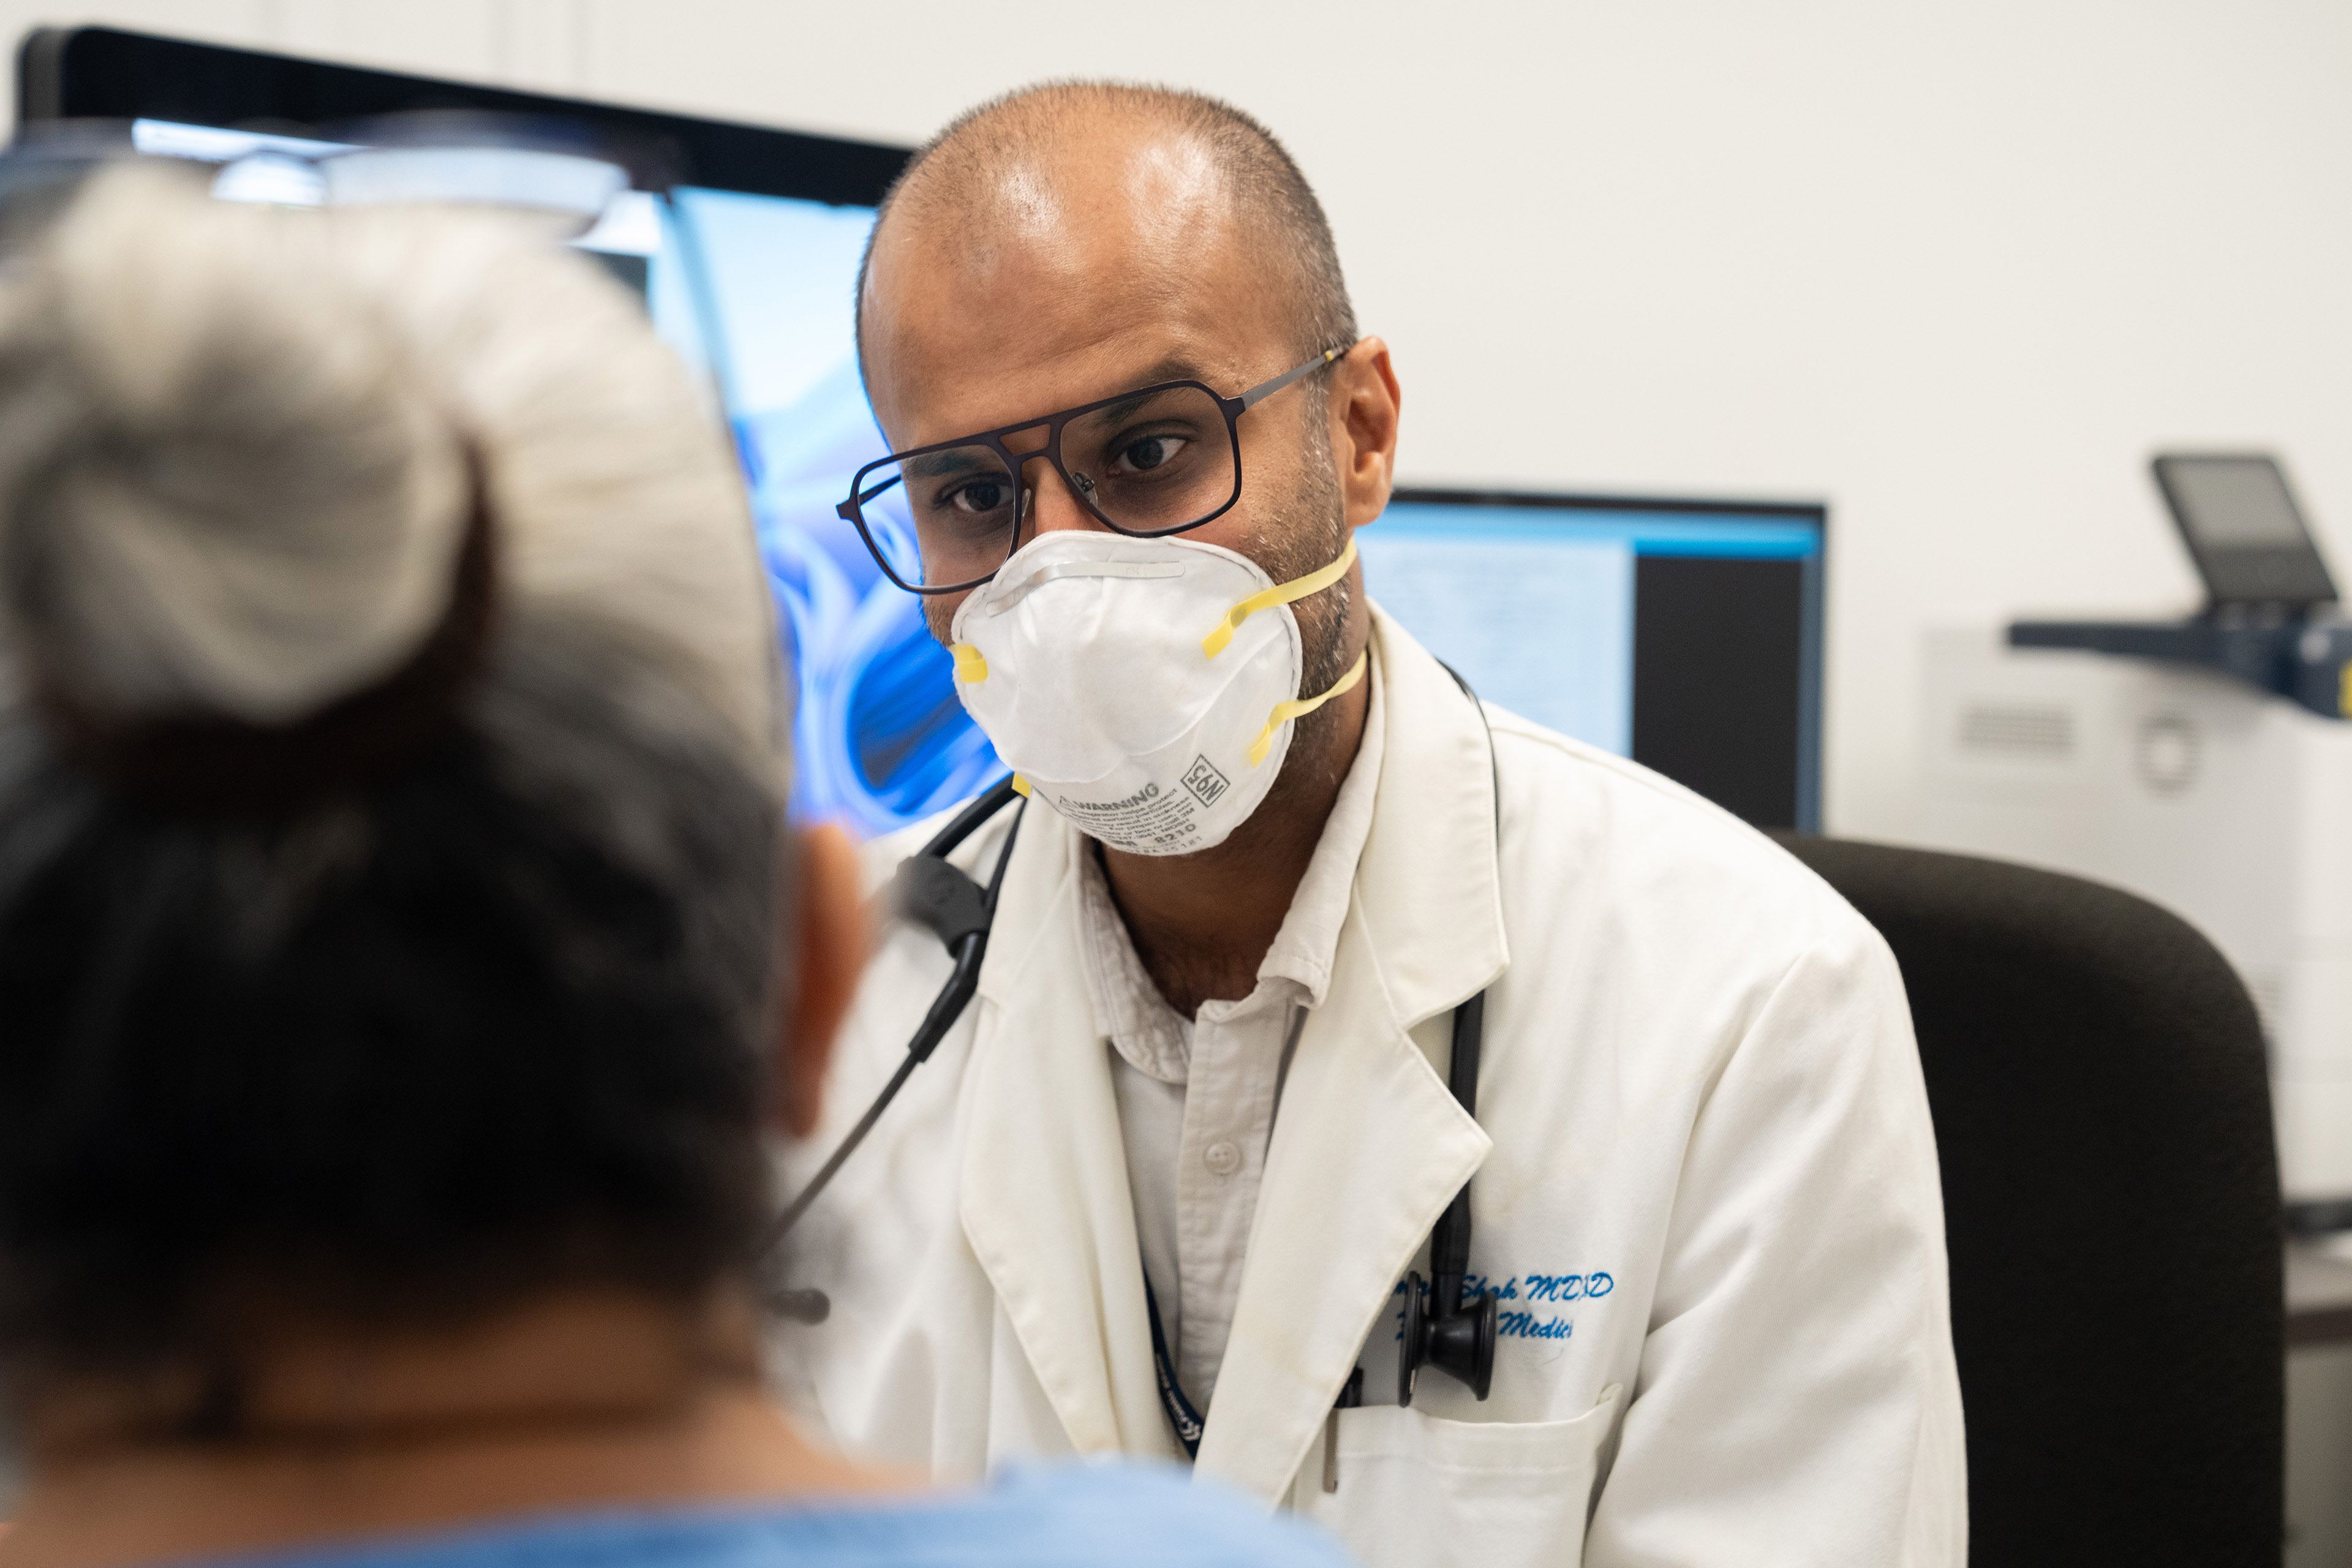
    A doctor wearing glasses and a facemask talks with a patient
    Naman Shah examines a patient at Monrovia Health Center, a Los Angeles County public health clinic in Monrovia, California. Shah says reducing medical debt in the community will depend on effective prevention strategies, just as stopping the spread of infectious disease does. (Lauren Justice for KFF Health News and Tradeoffs)

    Presumptive Eligibility

    One potential solution is a system that automatically screens and qualifies low-income patients for financial aid without requiring an application. This is called presumptive eligibility.

    Some hospitals already use such systems, which rely on software that checks patient eligibility based on publicly available information such as credit history.

    The strategy can be very effective. Shah said hospitals that have deployed presumptive eligibility systems have reported as much as a 50% increase in the amount of financial aid they give patients.

    Under a state law passed last year, all California hospitals will have to start doing presumptive eligibility screening by next July.

    But the systems can be expensive and difficult for smaller hospitals to implement. Only about 1 in 5 hospitals in Los Angeles County currently use them, Shah said.

    Public health officials wondered if they could help more hospitals set them up.

    The county, which, like many local governments, faces major fiscal challenges, couldn’t pay for this, Shah said. But the public health department could bring together healthcare and hospital officials in the county to figure out another solution.

    “The beauty of government is not when it always has to do the work,” Shah said. “We have the ability to make sure that people cooperate.”

    The Hospital Association of Southern California, initially wary of the county initiative, came to see improving hospital financial aid programs as beneficial to hospitals, many of which were wasting money on collections. “The billing process is cumbersome and costly,” said Paul Young, a senior vice president with the association.

    The association agreed to procure a presumptive eligibility system and make it available to its members. This bulk-purchasing approach, which Young compared to “a Costco model,” would lower the cost for individual hospitals, he said.

    At the same time, L.A. Care, a nonprofit health plan that administers Medicaid coverage for more than 2.5 million low-income county residents, committed $2 million to set up the system.

    The investment reflected the safety net insurer’s mission to make medical care accessible to more people, said Melanie Fontes Rainer, who leads strategic planning for L.A. Care. “It’s going to make Los Angeles County better,” she said.

    Making It Work

    Getting the new system up and running by January, as the partners hope, faces challenges.

    Hospital officials are figuring out how the system will be funded in the long term. And it’s unclear how many of the county’s 88 acute care hospitals will ultimately use it, even if it’s cheaper and easier to access.

    The partners are also working to improve data that the system relies on to screen patients. One goal is to link the system to tax records maintained by the state of California. This would provide hospitals with more accurate information on patients’ income than current systems, which often rely on estimated income.

    Walker, the patient advocate at Dollar For, said he’s heartened by the county’s effort. “I’m optimistic that we can make a better charity care system,” he said. “And the fact that hospitals in Los Angeles County are willing to be innovative and creative about ways we can do that is super encouraging.”

    For his part, Shah said county public health officials recognize that a better screening system at hospitals won’t by itself eliminate medical debt. But he said the public health department couldn’t ignore a problem that affects more county residents than asthma or tobacco use.

    “Prevention is our bread and butter,” he said.

    A doctor wearing a white coat and glasses, with a stethoscope around his neck, stands in a medical clinic hallway
    “The impacts of medical debt were staggering,” says Naman Shah, who since 2023 has led a Los Angeles County initiative to tackle the debt problem. (Lauren Justice for KFF Health News and Tradeoffs)

    This article is part of “Hidden Help,” an investigative series from Tradeoffs and KFF Health News about how hospitals can protect their patients from the life-altering harms of medical debt.

  • Opinion: How CMS plans to fix a major flaw in the 340B drug discount program

    Opinion: How CMS plans to fix a major flaw in the 340B drug discount program

    By Casey B. Mulligan

    Oct. 8, 2026

    Mulligan is the chief economist and chief regulatory officer at HHS.

    Some Medicare patients owe more in coinsurance than the hospital paid for their drug. That arithmetic sounds impossible. It is a consequence of the 340B drug discount program and Medicare’s payment formula. Now the Department of Health and Human Services, where I work, is proposing to narrow that gap.

    Congress created the 340B drug discount program in 1992 to financially support safety net hospitals that serve low-income patients. Drug manufacturers must give them steep discounts. But Medicare, Medicaid, and commercial insurers generally reimburse them at the full amount, allowing these hospitals to keep the spread above the discounted purchasing costs.

    A new report from the Department of Health and Human Services shows other unintended consequences of this well-intended program. The spread grows with the price of the drug. It therefore rewards hospitals for using more and costlier drugs and makes physician practices and infusion clinics more valuable after a 340B hospital acquires them. The patient’s treatment needn’t change. The owner and billing site do.

    The 340B program has exploded: Eligible drug purchases rose from $12 billion in 2015 to $81 billion in 2024, mostly at hospitals, as shown in the report. Those purchases are now larger than net Medicare Part B and Medicaid drug spending overall and, among public prescription drug programs, are smaller only than Medicare Part D.

    A 340B hospital that buys another hospital or a physician practice can register more off-campus clinics and contract pharmacies and capture more spread. Hospital off-campus clinic sites grew from about 7,000 in 2013 to more than 34,000 in 2023, often in neighborhoods that are wealthier and better-insured than that of the parent hospital. Contract pharmacies grew from roughly 1,300 in 2010 to more than 31,000 by mid-2026, dominated by the largest chains.

    With greater bargaining power after acquisitions, hospital systems can negotiate higher commercial prices for health care services, which can in turn raise premiums. Newly acquired hospital outpatient sites can also add facility fees to non-drug services. The effects of 340B show up as larger, more expensive hospital systems and a bigger bill for patients, employers, and taxpayers. The program’s ripple effects contribute to the broader problems facing the U.S. health care system.

    Medicare payment for Part B drugs is typically based on average sales price (ASP). Beginning in 2018, the first Trump administration narrowed the spread in Medicare by paying hospitals for 340B drugs’ ASP minus 22.5% rather than the usual statutory standard of ASP plus 6%, based on an earlier estimate of their average minimum discount.

    Overall outpatient drug payments rose nearly 15% a year from 2015 through 2017. Once the lower rate was fully in effect, inflation-adjusted payments largely plateaued. Payments for the affected 340B drugs held near $7 billion from 2019 through 2021. It is clear that Medicare payment policy influences outpatient drug spending.

    The Supreme Court ruled in 2022 that HHS couldn’t vary payment rates by hospital group without first conducting the acquisition-cost survey required by statute. The court didn’t find that hospitals were economically entitled to the markup. It found that HHS lacked a procedural prerequisite. After the lower rate ended and ASP plus 6% returned for these drugs, annual payments for the affected drugs rose from $7.1 billion in 2021 to $10.7 billion in 2023 — a $3.6 billion increase. Overall outpatient drug payments rose from $14.3 billion in 2021 to $17.6 billion in 2023.

    Restoring the higher rate meant paying hospitals more for the same drugs. The $3.6 billion increase combines that direct payment effect with induced changes in hospitals’ dispensing quantities and drug manufacturers’ underlying prices. The larger spread also strengthens hospitals’ incentive to choose costlier drugs and move treatment into 340B billing sites.

    Off-campus hospital departments benefited too. From 2021 to 2023, payments for their affected 340B drugs rose about $800 million even as claims fell and the number of beneficiaries remained similar. Although these amounts do not tell us how many practices hospitals acquired because of the markup, they indicate the additional financial incentives for acquisitions.

    On April 18, 2025, President Trump directed HHS to obtain the cost information the statute requires. CMS surveyed hospitals from January through April 2026 and has proposed paying for affected 340B drugs at ASP minus 33.4% in 2027. CMS estimates that Medicare drug payments would fall by $4.55 billion in the first year and beneficiary drug copayments by $1.15 billion.

    For a drug with an ASP of $1,000, a beneficiary’s standard 20% coinsurance would fall from $212 to $133.20. The prescription hasn’t changed. The patient’s share of the hospital’s bill has. Narrowing the spread also weakens the incentive to steer patients toward costlier drugs and to acquire physician practices and infusion clinics — the very behaviors that have made care more expensive.

    There’s an important lesson here. A small, well-intended discount for safety net hospitals became a large institutional subsidy with expensive unintended consequences. Under the proposed rule, hospitals would still receive their 340B drug discounts. What would change is Medicare’s payment for those drugs at affected hospitals. Congress provided for a survey of hospitals’ acquisition costs, and CMS says its proposed rate would “more accurately align Medicare payments with hospital drug acquisition costs.”

    Medicare patients should not pay coinsurance as though the discount did not exist.

    Casey B. Mulligan is the chief economist and chief regulatory officer at HHS.

  • Teladoc Health Adds Contactless Vitals and Ambient AI Scribe to Virtual Visit Platform

    Teladoc Health Adds Contactless Vitals and Ambient AI Scribe to Virtual Visit Platform

    telehealth telemedicine

    Teladoc Health announced Wednesday that it is launching two new AI-powered capabilities built into its Solo smart care platform for hospitals and health systems to be used during virtual visits. 

    SoloVitals, which captures patients’ heart rate and respiratory rate using only the camera on their device, will be available for private preview with select customers, with wider availability expected in December. The New York-based telemedicine company did not identify those customers. SoloScribe, an ambient, EHR-integrated documentation tool, is now generally available.

    Both tools integrate with the already-established Solo virtual care platform, so that the more than 15,000 global customers can smoothly integrate the new capabilities without the need to add new technology, according to the company’s news release. SoloVitals and SoloScribe aim to support patient care operations and reduce technology fragmentation across health systems so that providers can keep their focus where it’s truly needed – on the patient.

    “SoloVitals addresses a common gap many hospital virtual care teams experience, where they cannot collect real-time physiologic data from patients during a virtual visit,” said Joby McKenzie, general manager of North American health systems at Teladoc Health. 

    Danny Sanchez, vice president of technology and innovation at Teladoc Health, explained how SoloVitals collects patient vital signs contactlessly. 

    “During intake for a virtual visit, the patient uses the camera on their own device to capture supported vital signs of heart rate and respiration rate,” Sanchez said. “It uses remote photoplethysmography (“rPPG”) to detect very small changes in the color of the skin caused by blood flow. This data is combined with a computer vision assessment of patients’ fine movements and is then evaluated by sophisticated algorithms to return multiple physiologic measurements.”

    Results are then available for the provider before or during the virtual visit, offering real-time physiologic data which can help to inform care decisions. Sanchez noted that patients do not need to download a separate app, and that the process is guided by on-screen prompts to facilitate a smooth user experience. 

    SoloScribe offers ambient AI documentation – that alone is not unique, but what makes SoloScribe stand out is simple: it doesn’t require hospital systems to apply new technology. It works within the Solo platform that’s already integrated into the EHR – be it Epic or Oracle Health.

    “Most ambient scribe tools on the market ask hospitals to buy, install and manage one more piece of technology,” said Sanchez. “Our clients keep telling us they want the opposite: new capabilities built into the products and workflows they already know and use.”

    This goes to the heart of one of the biggest challenges health systems face today, that McKenzie identified as “technology fragmentation.” 

    She added that “each new capability comes with another vendor, another login, another device, or another workflow. The larger opportunity of integration is to help health systems move from a collection of disconnected tools to a more unified care environment.”

    Photo credit: Sorbetto, Getty Images

  • Constant Vigilance is the Watchword for Healthcare AI Governance 

    Constant Vigilance is the Watchword for Healthcare AI Governance 

    A webinar moderated by MedCity News Editor-in-Chief Arundhati Parmar delved into findings of the recently published Healthcare AI Readiness Index. Panelists discussed how best to balance AI adoption, governance, how to scale AI at healthcare institutions and best practices for doing so. Sponsored by Cotiviti, the webinar included perspectives from Cotiviti CIO Sean Warren and Thomasina Anane, Associate Vice President, Enterprise Analytics, with the Alliance of Community Health Plans.

    Cotiviti turns fragmented data into actionable insights. It helps healthcare organizations reduce waste, fraud, and abuse, and works with them to simplify their operations.

    “In many ways, what we’ve become is the connective tissue that helps healthcare work more efficiently across all of the payers, providers, and other stakeholders,“ Warren said.

    Anane referenced a recent annual meeting of ACHP, which included a candid discussion on AI governance.

    “One theme that really came through clearly is that AI governance has to start well before deployment and evolve along the use case. Many of our health plans are grappling with issues like: What is my state saying about AI use? What does that look like federally and what does that look like as a health plan?….What data are actually involved? What decision is being influenced? What happens when the output is wrong?”

    The biggest challenge with AI governance in a clinical and payer setting is the need for constant vigilance, a point made by both Anane and Warren. 

    “Deployment is really not the finish line,” Warren said. “It’s constant follow-up, constant security checks, and we have a lot of human-in-the-loop and human oversight with observability. It’s ten times more important when we add AI to the mix to be able to know what that AI is doing. Do you have the guardrails around what the AI is doing in your environment? Do you have the ability to undo it? Do you have the ability to follow and trace every transaction?” 

    The webinar discussion also touched on other issues such as:

    • What should leaders assess before moving an AI use case from pilot to enterprise deployment?
    • Are traditional vendor questionnaires and point-in-time assessments still sufficient?
    • What is driving shadow AI use?
    • Important considerations for Chinese AI models and frontier AI models.
    • Why might traditional cybersecurity controls be necessary, but insufficient in the new threat environment healthcare organizations face?

    To access a recording of the webinar, fill in the form below:

    Photo: Sandwish, Getty Images

  • STAT+: Are stem cell treatments about to have their day?

    STAT+: Are stem cell treatments about to have their day?

    You’re reading STAT’s D.C. Diagnosis newsletter

    Adobe

    John writes about the politics of health care, and he is the author of the twice-weekly D.C. Diagnosis newsletter. You can reach John on Signal at John_Wilkerson.07.

    You’re reading the web edition of D.C. Diagnosis, STAT’s twice-weekly newsletter about the politics and policy of health and medicine. Sign up here to receive it in your inbox on Tuesdays and Thursdays.

    Celebrity doctor Mike Varshavski has been contacted by The Bachelor for its 30th season. Send news tips and hot physicians to [email protected] or John_Wilkerson.07 on Signal.

    A lame lame-duck

    On Friday, President Trump said he will give $90 to more than 20 million seniors to help pay for Medicare premiums.

    STAT+ Exclusive Story

    Already have an account? Log in

    STAT+

    STAT+

    This article is exclusive to STAT+ subscribers

    Unlock this article — plus in-depth analysis, newsletters, premium events, and news alerts.

    Already have an account? Log in

    View All Plans

    To read the rest of this story subscribe to STAT+.

    Subscribe

    1. John writes about the politics of health care, and he is the author of the twice-weekly D.C. Diagnosis newsletter. You can reach John on Signal at John_Wilkerson.07.

  • Opinion: I’m a doctor. Here’s what I want the public to know about AI tools and health care costs

    Opinion: I’m a doctor. Here’s what I want the public to know about AI tools and health care costs

    When Blue Cross Blue Shield recently published research suggesting that hospitals use artificial intelligence tools to extract more money from insurers without providing additional care, people were mad. Amid growing concerns about AI, one glimmer of hope has been its potential to improve health — and yet, here it was: inflating health care costs without yielding any benefits.

    As a doctor who has used the kinds of tools being criticized, I’m frustrated, too: We can document honestly and still wind up inflating hospital bills. This is because comorbidities function as an on-off switch with respect to billing, even though they affect patient care in nuanced ways.

    Although the problem warrants a systemic fix, the best short-term solution is for hospitals to create more nuanced documentation tools, and for clinicians to exercise judgment when using them.

    What did the research show?

    BCBS suggested hospitals are using automated tools to document secondary diagnoses — like anemia, malnutrition, and low sodium — which allow them to charge more for caring for these patients.

    For instance, a patient might be admitted for diverticulitis (primary diagnosis), but found on post-op labs to have acute blood-loss anemia (secondary diagnosis). Hospitals can use these secondary diagnoses to label a patient as having a comorbidity or a complication, allowing them to bill more for the hospitalization, whether or not they treated the patient’s anemia. These “bump codes” have cost BCBS hundreds of millions of dollars over the past two years, and these costs are presumably passed along to patients in the form of higher premiums.

    BCBS claims that bump coding has become more widespread because hospitals are using AI tools to identify secondary diagnoses. Automated tools can skim a patient’s chart and prompt physicians to document that the patient is, for instance, anemic, and what they are doing about it.

    Are doctors to blame?

    A few weeks after I started medical residency, I began getting emails from hospital administrators I had never met, whose signatures said they were risk adjustment specialists. The emails were generic and polite, advising me to review clinical documentation integrity (CDI) queries on inpatients I was caring for. If I didn’t respond quickly, the request would be forwarded to the attending physician supervising me. A typical CDI query would point out that my note hadn’t commented on, say, a patient’s low sodium level, and would ask me to document that they had low sodium and what (if anything) we were doing about it.

    Like most residents, I was already spending far more time on my computer than I was with my patients. Soon, CDI queries streamed into my inbox with such regularity that I turned to a more senior doctor to ask how I might stave them off. That doctor showed me an automated tool that I could include in my notes. This tool would assess a patient’s lab results, automatically detect any additional diagnoses a patient had (like anemia, malnutrition, or low sodium), and prompt me to specify whether we were monitoring, evaluating, or treating.

    I assumed it was lucrative to the hospital for me to document these diagnoses (why else would they be paying risk adjustment specialists to email me about them?), but we almost always were at least monitoring the secondary diagnosis in question, and I accurately documented as much.

    Including this tool’s outputs in my notes kept the risk adjustment specialists from hounding me and won me back several minutes of each day — enough time to poke my head into a patient’s room before I went home, or call a patient’s family member to give a quick update. I always answered the questions included in my tool honestly, but in the back of my mind, I wondered whether I was doing my patients a disservice: Was I inflating the cost of their hospitalizations without actually improving their care?

    Where bump codes come from

    In general, hospitals are reimbursed for hospitalizing patients on the basis of diagnosis-related groups, or DRGs. DRG payments are set by the Centers for Medicare and Medicaid Services by analyzing claims data. (Medicare uses DRGs to set payments, while many commercial insurers, including BCBS, use the DRG system to negotiate reimbursement rates with hospitals.) Let’s say a patient is admitted with diverticulitis requiring surgery (typically billed as DRG 331 if there are no complications). CMS has estimated how much it usually costs to care for one of these patients and insurers prospectively pay hospitals on that basis; a hospital generally won’t get reimbursed more for keeping the patient longer, administering more drugs, placing more IVs, and so on.

    However, some hospitals care for sicker patients than others. The typical diverticulitis patient at a tertiary medical center in a poor area will require more support than a diverticulitis patient at a community hospital in an affluent area. The government does not want to penalize hospitals that see more complex patients, and so it allows hospitals to seek additional reimbursement forcomorbidities or complications that increase the cost of their care.

    This is where bump codes come from: Hospitals can bill more complex diverticulitis admissions as DRG 330, which is reimbursed at a higher rate. Not all comorbidities or complications count: In 2007, the last time DRGs were substantially changed, CMS analyzed claims data and used this analysis to decide which conditions qualify and set reimbursement rates. CMS pays hospitals more for patients with conditions like low sodium because it has found that it costs hospitals more to care for these patients (perhaps because they tend to be hospitalized longer and more often require ICU admissions).

    However, although CMS adjusts DRG payments from year to year, the list of bump codes hasn’t been overhauled in nearly two decades.

    Bump codes can help identify complex patients and ensure hospitals are paid more for caring for them. These are good things, in part because they reduce hospitals’ incentive to seek out healthier, more advantaged patients. While BCBS claims that hospitals are increasingly using these codes to bill more without actually providing more care, hospitals would presumably counter that they were being insufficiently reimbursed before, and that their coding is accurate. After all, the BCBS study does not claim that hospitals are engaging in fraud; the question is just whether the lab abnormalities hospitals are billing for warrant higher reimbursements.

    So who’s right?

    This issue boils down to the following question: How much more does it cost to care for a patient with a secondary condition, and do current coding rules accurately reflect this?

    The answer is that it depends. For instance, not all low sodium levels are created equal. If a patient briefly has a sodium level that falls below the normal range, but their sodium immediately corrects once they’re able to eat again, they probably don’t require any additional resources, and hospitals shouldn’t be reimbursed more for caring for them.

    By contrast, a patient with dangerously low sodium levels requiring an ICU stay, frequent lab checks, and carefully titrated IV fluids undoubtedly does use more resources.

    This leaves doctors in a tough spot: Risk adjustment specialists ask us to document real diagnoses that we know could increase the cost of a patient’s bill, but we have no idea by how much. Moreover, there’s no medical school module on how much any of these comorbidities affects the true cost of the hospitalization. Against this backdrop, it makes sense that doctors try to just tell the truth: yes, this patient has low sodium, and we are monitoring it, even though this probably allows hospitals to code some patients as being more resource-intensive than they truly are.

    What we can agree on

    This entire enterprise — risk adjustment specialists spamming doctors, who are already nose-deep in documentation burden, to document diagnoses that often do not affect patient care, while insurers publish reports that fail to capture the nuance of the issue, leaving the public angry and confused — highlights a more general problem with respect to how the U.S. health care system works.

    By design, hospitals and insurers are meant to compete with each other, with hospitals trying to collect as much money as they can for providing care, and insurers trying to pay as little as possible. Hospitals bolster their side by hiring risk adjustment specialists and employing AI tools, while health insurers hire payment integrity specialists and employ different AI tools.

    Patients lose out because the administrative bloat inflates the cost of medical care, while making costs less transparent and harder to contest. Ultimately, the fix should be structural: At a minimum, we need to overhaul the list of secondary conditions that are eligible for bump coding. CMS attempted to do this in 2019, when it proposed downgrading or eliminating many bump codes based on new data showing they were not associated with increased costs. But hospitals pushed back, and the effort eventually stalled.

    What should we do in the meantime?

    Secondary diagnoses are supposed to be billed only when they are clinically significant — for instance, when they require further evaluation, treatment, diagnostic procedures, or monitoring. But in practice, the bar for clinical significance is probably lower than it should be. (Even rechecking a lab may qualify as monitoring.) Accordingly, I suspect the BCBS study is tracking a real problem, and that much of the documentation of secondary diagnoses isn’t linked to patient complexity.

    Early in residency, I was caring for an immunosuppressed patient who kept spiking fevers. My colleagues and I wondered whether he might have an indolent infection lurking somewhere and ordered an echocardiogram to rule out endocarditis. His heart valves showed no signs of bacterial growth, but trace backflow was detected across one of his valves, a finding present in most people.

    Soon, I received a CDI query inviting me to document his valve dysfunction in my note. I did not do this, because his incidental valve finding was irrelevant to his hospitalization. Instead, I typed out a response indicating as much. However, it would have been easier and quicker to click through the check boxes, and, despite answering them honestly, potentially inflate the patient’s bill.

    At least some CDI tools built into electronic medical records — including the one I have used — default to including secondary diagnoses in ways that are likely to lead to bump coding. One way to improve the status quo would be to ensure that such tools give physicians the option to document whether a secondary diagnosis is clinically significant or not, rather than simply asking them how they are addressing it (on the presumption that it is clinically significant).

    Hospitals should build such tools, and regulators should ensure they do. In the meantime, I’ll exercise clinical judgment when using my CDI tool — if the low sodium seems important, I’ll document it, and if it doesn’t, I’ll politely decline when a risk adjustment specialist invariably asks me to.

    Leah Pierson is a resident physician.

  • STAT+: New Trump regulations would clean up health care pricing disclosures

    STAT+: New Trump regulations would clean up health care pricing disclosures

    Public drug price information is now coming next year, Trump officials say

    Mehmet Oz at a federal event on Monday in Washington announcing new health care price transparency rules.Finn Gomez/Getty Images

    By Bob Herman

    Oct. 5, 2026

    Bob Herman is the author of Health Care Inc., an award-winning weekly newsletter about the business of health and medicine.

    Bob covers the money in health care, focusing on health insurance and hospitals. His stories delve into Medicare Advantage, opaque prescription drug benefits, and how much executives actually make. He is also the author of the Health Care Inc. newsletter. You can reach Bob on Signal at bobjherman.09.

    The Trump administration released new regulations Monday that will force health insurance companies to publish cleaned-up spreadsheets of the prices that they pay hospitals and doctors, while stripping out meaningless data that clogged up the files.

    Trump officials also said they will start developing the system for disclosing prescription drug prices next month. A “hopeful” final plan for drug pricing data will come out by next May, said Mehmet Oz, the head of Medicare and Medicaid, at an event Monday. The government will enforce those requirements by the end of 2027. 

    Last year, the Trump administration punted on finalizing drug price disclosure rules, in a victory for drug companies and pharmacy benefit managers that have fiercely guarded their prices. 

    STAT+ Exclusive Story

    Already have an account? Log in

    STAT+

    STAT+

    This article is exclusive to STAT+ subscribers

    Unlock this article — plus daily intelligence on Capitol Hill and the life sciences industry — by subscribing to STAT+.

    Already have an account? Log in

    View All Plans

    To read the rest of this story subscribe to STAT+.

    Subscribe

    1. Business of Health Care Reporter

      Bob covers the money in health care, focusing on health insurance and hospitals. His stories delve into Medicare Advantage, opaque prescription drug benefits, and how much executives actually make. He is also the author of the Health Care Inc. newsletter. You can reach Bob on Signal at bobjherman.09.

  • Hospitals Have a Little-Known Tool To Prevent Medical Debt. Here’s How It Works.

    Hospitals Have a Little-Known Tool To Prevent Medical Debt. Here’s How It Works.

    If you have medical debt, there’s a good chance you owe money to a hospital.

    One way patients can avoid medical debt is through hospital financial assistance, also known as charity care. Most of the nation’s hospitals offer free or discounted medical care to patients with very high medical debt or low incomes.

    Getting financial assistance, however, can be challenging. Many patients don’t know that hospitals offer financial help, surveys show, and complex application forms leave others stymied.

    Hospitals often demand that applicants turn over bank statements, pay stubs, tax returns, divorce filings, or other materials, and submit their applications in person, by mail, or by fax.

    “They don’t make it easy,” said Neale Mahoney, a Stanford University economist who studies medical debt.

    Such hurdles leave many patients with unpaid bills they should never have had to pay in the first place. In a single year, hospitals and health systems billed patients for at least $2 billion that they likely didn’t owe, one analysis found.

    As healthcare costs climb and more people lose their coverage, states and hospitals are testing an emerging approach to fix this problem: automatically screening patients to see if they qualify for assistance and proactively wiping out debt when they do. This is known as “presumptive eligibility.”

    Under this approach, patients may have the cost of their care wiped out before they see any bills — but not always. Hospitals differ on when, how, and for whom they use auto-enrollment, potentially impinging on patients’ finances.

    Here’s what you need to know about how auto-enrollment works.

    What is hospital financial assistance?

    In many states, hospitals set their own criteria for whom they provide financial aid. Eligibility is typically based on income for the patient’s entire household. The closer patients are to poverty, the less they have to pay. Patients with middle incomes and insurance are sometimes eligible for discounts, especially if their bills would gobble up a big chunk of what they earn.

    At least 11 states require hospitals to wipe out bills for low-income patients, though income cutoffs vary. Georgia, for example, mandates free care for anyone with income slightly above the federal threshold for poverty. In several states — including Oregon, North Carolina, and Maryland — patients can earn double that amount and still get free care.

    But in most states, many patients must complete applications to receive assistance.

    Several states in recent years have launched investigations and passed legislation designed to make it easier for people to get help. Research into medical debt, however, suggests gaps persist.

    How many hospitals use auto-enrollment?

    Nearly all nonprofit hospitals say they screen and automatically reduce bills for certain patients.

    Under the Affordable Care Act, nonprofit hospitals must make reasonable efforts to find people who are eligible for help before they take patients to court, sell their debt to collection agencies, or ding their credit over bills. Presumptive eligibility is one way hospitals can comply with the regulation, which took effect in 2016.

    In the first year under the new rules, about 70% of tax-exempt hospitals nationwide said they screened patients and proactively reduced bills, according to an analysis of federal data for Tradeoffs by the independent research institute RTI International. As of 2022, that figure was nearly 90%.

    The federal law doesn’t apply to for-profit and public hospitals, which don’t have to report the actions they take before going after patients for unpaid bills.

    In six states, policymakers require hospitals to use presumptive eligibility and skip applications for certain patients. Those states are California, Delaware, Illinois, Maryland, North Carolina, and Oregon.

    Who is eligible to be automatically enrolled in financial assistance?

    In most states, hospitals decide which patients can skip the application.

    Common groups automatically screened include people who are homeless, deceased, or already enrolled in state or federal programs to help low-income households with housing, food, or prescriptions. Other hospitals have more unique criteria, like Christus Health, which will write off bills for anyone in a religious order who took a vow of poverty.

    Eligibility criteria are often buried in official policies and hard to find or decipher. Some hospitals share little to no public information about whom they will proactively screen. Thirteen hospitals owned by Ascension, one of the nation’s largest Catholic health systems, state only that they may screen patients “with a sufficient unpaid balance.”

    Across the half-dozen states with presumptive eligibility mandates, eligibility rules vary. Maryland, for example, requires hospitals to proactively wipe out bills only for patients who already get government help for food or utilities but are ineligible for Medicaid. In Illinois, lawmakers created less-stringent requirements for rural hospitals compared with urban facilities.

    In Oregon, starting in 2024, hospitals had to screen anyone who owed more than $500 and every patient on Medicaid or who is uninsured. In 2025, roughly 80% of Oregon patients who got financial help with bills never filled out an application, based on data shared publicly by the first 26 hospitals to do so. The state’s legislature this year raised the screening threshold to include patients who owe at least $1,500 for a single visit.

    Without an application, how do hospitals figure out who gets help?

    Hospitals have several ways to find patients eligible for financial assistance.

    Typically, hospitals turn to public records, any information patients have previously volunteered, or tools from consumer credit companies to estimate whether patients qualify to have bills reduced.

    For example, if a hospital sees that a patient lives in a high-poverty ZIP code or has no address listed, that could be enough to deem them eligible. Many pay companies to run employment and credit checks on patients to determine whether they qualify for free care.

    Hospitals may also consider how likely patients are to pay bills, regardless of how much they earn. This is called “propensity to pay.” California and Oregon prohibit its use, concerned that hospitals may try to collect more often from people who dutifully pay their bills even though their incomes qualify them for financial assistance.

    When do hospitals screen patients for financial aid?

    It depends.

    Illinois, North Carolina, and Oregon require hospitals to screen certain patients before they send any bills. California hospitals will have to do the same starting in 2027.

    Some hospitals voluntarily screen patients before sending bills; others try to collect money from patients first. As long as they screen patients before suing them for very overdue bills, hospitals can stay within the letter of the federal law that pushed many of them to embrace presumptive eligibility.

    For example, the policy of Christus Health is to screen patients only “after all other eligibility and payment sources have been exhausted.”

    Anna Stelter, vice president of policy for the Texas Hospital Association, said hospitals want to investigate other options for payment — like Medicaid or county safety net programs — before they give out financial assistance.

    “We do want to make sure that whoever is financially responsible for that care is identified and pays,” Stelter said. “Charity care is the relief of last resort.”

    Hospitals’ publicly posted policies may also be fuzzy about when they will screen for patients likely eligible for help. For example, Cook Children’s Health Care System in Fort Worth, Texas, says its goal is to determine a patient’s eligibility “as soon as sufficient information is available.”

    Who pays the bills when patients get free care?

    In one sense, we all do. Taxpayers cover some or all of the cost of financial assistance, though the amount varies by hospital.

    About half the nation’s hospitals are nonprofit and legally get a pass on paying most taxes. KFF estimates that nonprofit hospitals pocketed $24 billion in 2020 that they would otherwise have paid as income, sales, or property taxes.

    Government-owned and for-profit hospitals have their own sets of tax benefits to help offset costs for low-income patients. Government hospitals often get additional taxpayer support, and for-profit hospitals generally receive smaller government subsidies, like additional payments for caring for high numbers of uninsured and Medicaid patients.

    Whether taxpayer dollars fully cover hospitals’ costs for financial assistance depends on the amount of government support they receive — information often not publicly available. It also hinges on how many patients need help, how many meet hospitals’ criteria for assistance, and how many get through an application. Research shows hospitals spend widely different amounts on financial assistance, from less than 1% of yearly expenses to more than 7%.

    Philanthropy and hospitals’ income cover costs not absorbed by tax dollars.

    This article is part of “Hidden Help,” an investigative series from Tradeoffs and KFF Health News about how hospitals can protect their patients from the life-altering harms of medical debt.

    Melanie Evans is a reporter for Tradeoffs, a nonprofit newsroom reporting on healthcare’s toughest choices. Sign up for the weekly newsletter to get the latest stories every Thursday morning.

    Tradeoffs’ reporting for this series was supported, in part, by the California Health Care Foundation, the National Institute for Health Care Management Foundation, and the Solutions Journalism Network.